
Best Practices for Cross-Contamination Risk Assessment at Multi-Product Biologic Drug Substance Manufacturers

A multi-product facility does not become safe because every room is classified, every hose is labeled, and every changeover has a completed checklist. It becomes safe when the organization can make, and defend, a scientifically coherent claim that material from Product A cannot reach a patient receiving Product B at a level capable of causing harm.

That claim is harder to sustain in a contract development and manufacturing organization than in a conventional single-product facility. A CDMO must accommodate changing client portfolios, incomplete early-phase knowledge, different cell substrates and processes, short campaigns, accelerated technology transfers, and commercial pressure to use the same suites efficiently. Each new product changes the contamination problem. Each new process train changes the pathways. Each new piece of toxicological or clinical information may change what “acceptable” means.

The central task is therefore not simply cleaning validation. It is cross-contamination risk management across the product, process, facility, equipment, and patient-safety lifecycles.

For a multi-product CDMO, that system must distinguish clearly between two manufacturing architectures:

  • Reusable equipment, where previous-product carryover is controlled principally through equipment design, validated cleaning, sampling, analytical capability, maintenance, and changeover discipline.
  • Single-use systems (SUS), where direct carryover through the discarded product-contact path may be greatly reduced, but risk shifts toward assembly integrity, incorrect connections, retained reusable interfaces, extractables and leachables, particulates, supplier controls, sterilization assurance, and human manipulation.

Neither architecture is inherently safe. Both can be made safe. Both can fail in characteristic ways.

The Regulatory Question

The regulatory question is not, “Was the equipment cleaned?” It is, “Was the risk of cross-contamination identified, scientifically evaluated, controlled, and kept under review?”

ICH Q9(R1) defines quality risk management as a systematic process for assessing, controlling, communicating, and reviewing risks to product quality across the lifecycle. It also makes two points that matter directly to a CDMO: risk evaluation should be grounded in scientific knowledge and linked ultimately to patient protection, and the level of effort, formality, and documentation should be commensurate with risk. Resource limitations are not a valid reason to lower the formality of the assessment.

EU GMP Chapter 5 is more explicit about shared manufacture. It requires cross-contamination risk to be assessed, including contamination arising from product residues, aerosols, organisms, genetic material, and operators’ clothing. It further requires a quality risk management process that includes potency and toxicological evaluation and considers facility and equipment design, personnel and material flows, microbiological controls, physicochemical characteristics, cleaning processes, analytical capability, and the intended use of the product.

The EMA health-based exposure limit guideline replaces arbitrary carryover conventions with a structured scientific evaluation of pharmacological and toxicological data. A permitted daily exposure, or equivalent health-based exposure limit, represents a substance-specific daily exposure that is unlikely to cause an adverse effect over a lifetime; its derivation includes hazard identification, selection of the critical effect and point of departure, and application of adjustment factors for uncertainty.

FDA requirements approach the problem through enforceable expectations for buildings, flow, defined areas, equipment, procedures, and controls that prevent contamination and mix-ups. Under 21 CFR 211.42, material and product flow must be designed to prevent contamination, and operations must occur in defined areas or under other adequate control systems. FDA’s inspection program for protein drug substances also expects validated cleaning of nondisposable product-contact equipment, predetermined carryover limits for shared equipment, continued verification, and toxicologically derived acceptable daily exposures for highly potent or toxic residues; where limits cannot be achieved, dedicated or disposable equipment may be necessary.

For CDMOs, regulatory responsibility cannot be outsourced through the commercial contract. FDA’s quality-agreement guidance expects the owner and contract facility to define and document their respective CGMP responsibilities, but the agreement is a governance mechanism and not a transfer of accountability away from either party.

Begin With the Patient

The most common weakness in shared-facility risk assessments is that they begin with the room or equipment rather than the patient. The team draws process maps, scores hose connections, reviews cleaning cycles, and concludes that controls are strong. Only later, sometimes after the manufacturing decision has already been made, does anyone ask how much of the previous product could safely reach the next patient.

That sequence is backward.

The assessment should begin with a human product-safety evaluation for each molecule proposed for the facility. In EU terminology this is generally expressed through an HBEL, commonly a PDE or ADE. The evaluation is not merely a calculation and should not be reduced to a spreadsheet populated from the lowest clinical dose. It is an expert interpretation of all relevant pharmacological, toxicological, nonclinical, and clinical evidence.

EMA states that HBELs should be established for medicinal products and periodically reassessed as knowledge develops. It also specifies that the person deriving the HBEL should have adequate expertise and experience in toxicology or pharmacology, familiarity with pharmaceuticals, and experience establishing health-based limits. When the work is outsourced, the manufacturer must qualify the provider and the specific expert; simply purchasing an HBEL report without assessing the contractor’s suitability is not acceptable.

A defensible assessment should address, as applicable:

  • Molecular target and mechanism of action.
  • Intended and reasonably foreseeable off-target pharmacology.
  • Potency and dose-response relationships.
  • Route of administration and systemic bioavailability.
  • Patient population, including vulnerable or immunocompromised groups.
  • Acute, repeated-dose, reproductive, developmental, genotoxic, carcinogenic, immunotoxic, and local-tolerance information, where relevant.
  • Cytokine-release, immune agonism, immune suppression, complement activation, or unintended tissue cross-reactivity.
  • Clinical adverse-event data and the lowest exposure associated with the critical effect.
  • Pharmacokinetics, persistence, accumulation, and half-life.
  • Uncertainty arising from limited data, especially for early clinical programs.
  • The biological activity of fragments, aggregates, conjugated species, degradants, or process-transformed residues.
  • Whether route-to-route extrapolation is scientifically justified.

For biologics, the assessment may require judgment different from that used for a conventional small molecule. A protein may denature during alkaline cleaning, but “denatured” is not automatically synonymous with “non-hazardous.” Loss of the primary mechanism of action does not by itself establish the absence of immunogenic, inflammatory, allergenic, or other biological effects. Conversely, a large protein’s poor oral bioavailability may materially reduce risk for an orally administered next product, while offering little reassurance when the next product is parenteral. The conclusion must follow the exposure scenario and evidence, not a generic statement that proteins are readily degraded.

The resulting HBEL is an input to risk management, not the risk assessment’s conclusion. EMA explicitly states that once the health-based assessment is complete, the data should be used through QRM to determine whether existing technical and organizational controls are adequate or require supplementation.

The CDMO Information Problem

A sponsor often knows more about its molecule than the CDMO. The CDMO knows more about its facility, equipment, cleaning history, operators, and failure modes. A valid assessment requires both bodies of knowledge.

The sponsor should provide either a complete, reviewable HBEL assessment or the data needed for the CDMO to perform one. EMA expects the assessment, data references, and relevant expert information to be available during inspection. The quality agreement should therefore define ownership and timing for:

  • Provision and approval of the HBEL or toxicological monograph.
  • Disclosure of new clinical, nonclinical, or pharmacovigilance information.
  • Assessment of novel modalities, conjugates, linkers, payloads, or unusually potent mechanisms.
  • Product and process characterization relevant to cleanability and detectability.
  • Analytical reference standards and product-specific assays.
  • Review of cleaning limits and product-family placement.
  • Approval of shared-use, campaign, dedication, or exclusion decisions.
  • Notification when new information could invalidate the existing assessment.

This exchange must occur before facility fit is approved and not after the batch slot has been commercially committed. A CDMO that accepts a product before it understands the patient-safety boundary has allowed scheduling to precede science.

Hazard Is Not Risk

Cross-contamination discussions often collapse hazard and risk into one concept. They are not the same.

Hazard is the inherent capacity of the contaminant to cause harm. For a biologic drug substance, that may arise from potent pharmacology, immune modulation, sensitization, tissue cross-reactivity, or biologically active variants. Risk depends on both that hazard and the probability and extent of patient exposure through a credible contamination pathway.

This distinction matters because two products with similar HBELs may require different controls. A readily soluble biolgic processed in a closed, disposable flow path presents a different exposure likelihood from a sticky, difficult-to-detect protein processed through open transfers and a complex reusable skid. Likewise, the same previous product may present different risks depending on the next product’s route, maximum daily dose, batch size, population, and shared surface area.

The risk question should therefore be written explicitly:

Given the hazard of the previous product, the vulnerability and exposure of the next product’s patient population, the manufacturing sequence, and all credible transfer routes, are the proposed controls capable of maintaining carryover below a scientifically justified safe level with an adequate operating margin, even when foreseeable failures occur?

That final clause is important. A risk assessment that assumes every procedure is followed perfectly is not assessing risk. It is describing the intended state.

Map Every Transfer Route

The assessment should follow contamination as though it were tracing dye through the facility. Product residue does not recognize departmental boundaries, validation packages, or ownership charts.

At minimum, evaluate these pathways:

  • Direct product-contact carryover through shared tanks, columns, skids, piping, valves, pumps, sensors, transfer panels, and filling paths.
  • Indirect transfer from external equipment surfaces, carts, tools, hoses, parts, balances, bins, and mobile equipment.
  • Airborne transfer through aerosols, droplets, powders, open manipulations, pressure cascades, or HVAC recirculation.
  • Personnel transfer through gloves, gowns, footwear, tools, notebooks, radios, and movement between suites.
  • Material and waste transfer through staging areas, elevators, corridors, pass-throughs, cold rooms, and wash areas.
  • Mix-up through labels, status identification, electronic recipes, tubing connections, sampling materials, and component reconciliation.
  • Microbial or adventitious-agent transfer through shared utilities, insufficient segregation, retained moisture, open operations, or pre-viral and post-viral process crossover.
  • Laboratory transfer through shared sample-preparation areas, instruments, standards, retain storage, or incorrect sample identity.
  • Maintenance transfer through tools, removed components, lubricants, temporary hoses, bypasses, and post-maintenance restoration.

WHO guidance for biological products emphasizes QRM-based movement restrictions, logical and unidirectional flows, closed systems, qualified single-use components, and controls for open manipulations. It also warns against cross-use of certain reused components and highlights separation between activities with different biological risks.

The result should be a facility-wide contamination pathway map connected to process steps and equipment boundaries. A list of hazards without a spatial and temporal model of transfer is incomplete.

Select the Right Tool

No single risk tool is sufficient for the whole problem.

ToolBest useLimitation
Process and contamination-pathway mappingShows where product, people, materials, waste, air, and equipment intersectDoes not quantify control strength by itself
FMEA or FMECAEvaluates equipment- and step-specific failure modesRisk-priority numbers can hide severe events and create false precision
HACCPIdentifies critical points where control is essentialCan become too linear for complex facility-wide transfer pathways
LOPATests whether independent protection layers adequately reduce a defined scenarioRequires genuine independence and defensible failure assumptions
Fault-tree analysisWorks backward from a contamination outcome to combinations of causesCan become resource-intensive and difficult to maintain
Bow-tie analysisConnects threats, preventive controls, event, mitigations, and consequencesMay oversimplify technical detail unless supported by deeper assessments

ICH Q9(R1) permits different tools and degrees of formality but expects the approach to reflect uncertainty, importance, and complexity. In a multi-client CDMO, the most effective architecture is usually layered: pathway mapping at the facility level, FMEA for equipment and operations, and LOPA or bow-tie analysis for high-consequence scenarios.

Detectability should be used cautiously. A highly sensitive release test does not prevent cross-contamination, and routine product testing rarely provides enough sampling coverage to compensate for weak containment or cleaning. Detection controls can reduce uncertainty, but they should not be allowed to dominate the score merely because a method exists.
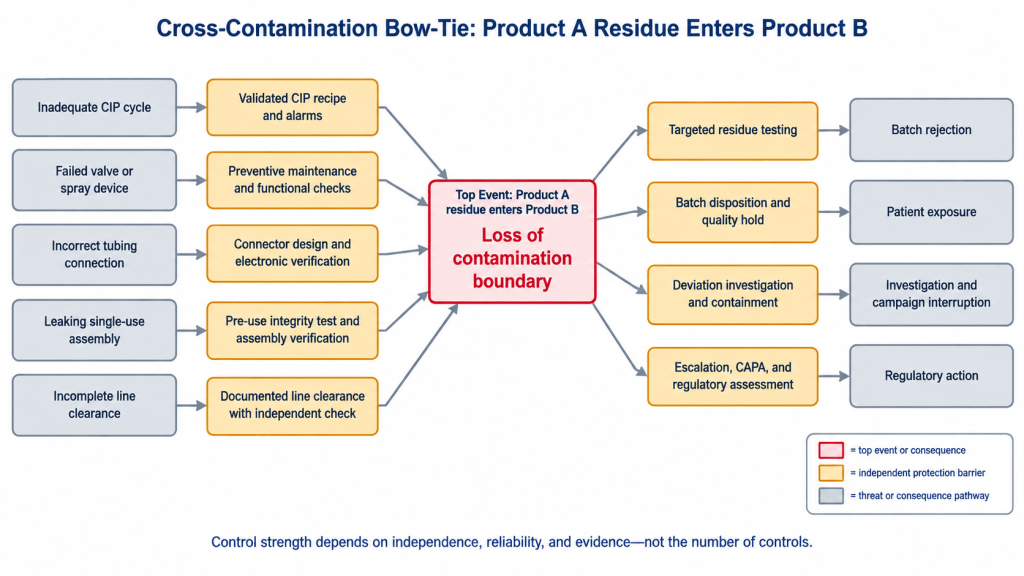
Bow-tie risk analysis showing how CIP failure, equipment faults, incorrect connections, single-use leaks, or incomplete line clearance can allow Product A residue into Product B, with preventive and mitigation barriers between threats, the loss of containment, and patient or regulatory consequences.

The Contamination Pathway and the Equipment Boundary

Reusable stainless equipmentSingle-use assembly
Fixed tank, piping, valves, CIP skidDisposable bag, tubing, connectors, filters
Main risk: retained product residueMain risks: assembly, integrity, E&L, mix-up
Primary assurance: validated cleaningPrimary assurance: supplier qualification and integrity
Key failure modes: dead legs, poor CIP coverage, failed valvesKey failure modes: leak, pinhole, wrong connection, package breach

Reusable Equipment

Reusable stainless-steel systems make the contamination boundary visible. The previous product contacted the equipment; the equipment will contact the next product; therefore, the organization must demonstrate that the transition is safe.

The principal controls are equipment design, defined cleaning procedures, validated cleaning performance, validated sampling and analytical methods, controlled dirty and clean hold times, inspection, preventive maintenance, status control, and periodic verification. FDA expects written cleaning procedures, predefined protocols, sensitive analytical methods, recovery studies, documented results, and management-approved conclusions that residues have been reduced to acceptable levels.

A reusable system assessment should examine:

  • Product-contact surface area and materials of construction.
  • Dead legs, low points, shadowed spray areas, valve bodies, diaphragms, gaskets, seals, and instrument ports.
  • Surface roughness, weld quality, drainability, slope, and retained-volume risk.
  • CIP coverage, flow, turbulence, spray-device performance, temperature, chemistry, concentration, time, and final-rinse endpoints.
  • Manual interventions and disassembly requirements.
  • Ability to inspect hard-to-clean locations.
  • Dirty-hold and clean-hold conditions.
  • Residue degradation or fixation during heat, drying, storage, or cleaning.
  • Microbial proliferation and endotoxin risk in retained moisture.
  • Maintenance failure modes such as blocked traps, failed valves, misaligned spray devices, sensor drift, or recipe changes.

Worst-case selection must be multidimensional. The lowest HBEL may identify the most hazardous product, but it may not be the hardest to remove. The most difficult cleaning challenge may instead be driven by solubility, concentration, viscosity, aggregation, drying behavior, adsorption, equipment geometry, or interaction with the cleaning agent. Health Canada’s guidance identifies HBEL, cleanability, solubility, physical characteristics, and prior experience among relevant worst-case factors and expects cleaning methods to be capable of measuring residue below the selected limit.

Cleaning limits

The HBEL for the previous product is translated into a maximum safe carryover for the next product using next-product batch size and maximum daily dose. That allowable mass is then allocated across the actual shared product-contact surface and converted into swab, rinse, or other sampling limits. The calculation must account for the entire shared process train and avoid allocating the same allowable carryover independently to multiple pieces of equipment.

The final operational limit should be no higher than the health-based limit and may need to be lower because of analytical capability, process control, variability, visual detectability, or company policy. “Visually clean” remains useful as an immediate gross-failure check but cannot replace a health-based and analytically verified criterion for product changeover.

The cleaning validation package should integrate:

  • Laboratory cleanability and degradation studies.
  • Coupon recovery for each relevant material of construction.
  • Swab and rinse method suitability.
  • Product-specific or scientifically justified nonspecific analytical methods.
  • Method specificity against degradants and cleaning-agent interference.
  • Worst-case locations selected from design and process knowledge.
  • Hold-time studies.
  • Automated recipe and alarm challenge.
  • Replicate validation runs under defined worst-case conditions.
  • Ongoing verification and periodic review of process capability.

A failed result cannot be repaired by repeated sampling until a passing value appears. FDA warns that routine “test until clean” behavior may demonstrate that the process is not validated rather than provide assurance of cleanliness.

Single-Use Systems

Single-use technology changes the risk architecture; it does not eliminate contamination control.

A fully disposable, closed product-contact path can sharply reduce the direct previous-product residue pathway because the contacted components are discarded rather than cleaned for the next product. It can also reduce cleaning-validation burden for those specific components. But the facility still contains reusable interfaces, support equipment, rooms, biosafety cabinets, external surfaces, transfer devices, sensors, exhaust pathways, and operators. The critical question becomes: Where does the disposable boundary begin and end?

EU GMP Annex 1 defines SUS broadly to include bags, filters, tubing, connectors, valves, bottles, and sensors and requires SUS-specific risks to be assessed within the contamination control strategy. Those risks include product-surface interactions, extractables and leachables, fragility relative to fixed systems, manual operations and connections, assembly complexity, holes and leakage, packaging opening, filter integrity, and particulate contamination.

A useful comparison is:

Risk dimensionReusable equipmentSingle-use system
Previous-product residueControlled by validated cleaningReduced where the complete contacted path is discarded
Main validation burdenCleaning process, sampling, analytical method, hold times, CIP performanceSupplier, sterilization, assembly, integrity, connection, shipping, installation, and use qualification
Typical hidden boundaryValves, seals, dead legs, skid piping, probesReusable probes, housings, manifolds, pumps, clamps, transfer ports, support vessels
Human contributionManual cleaning, assembly, inspection, status controlUnpacking, inspection, installation, connection, manipulation, and line clearance
Material interactionCorrosion, adsorption, surface condition, cleaning-agent compatibilityExtractables, leachables, adsorption, absorption, reactivity, and particles
Failure signatureResidue, retained liquid, ineffective cycle, maintenance degradationPinholes, leaks, misconnections, wrong assembly, compromised package, weld failure
Lifecycle dependenceEquipment maintenance and cleaning-state controlSupplier change control, lot consistency, irradiation or sterilization assurance, logistics

The boundary problem

The term “single-use process” is often applied too casually. A disposable bag connected to a reusable chromatography skid is not a completely single-use process. Neither is a disposable bioreactor connected through reusable probes or a stainless transfer panel. Every reusable product-contact or potentially product-contact interface must be identified and assigned an appropriate cleaning, sterilization, dedication, or disposal strategy.

Hybrid systems deserve particular scrutiny because responsibility can fall between programs. The cleaning-validation team may assume the flow path is disposable, while the SUS qualification team may assume reusable interfaces are covered elsewhere. The risk assessment should include a boundary diagram showing:

  • All direct product-contact components.
  • Indirect contact and splash-exposure surfaces.
  • Sterile boundaries and connection points.
  • Reusable sensors, housings, and hardware.
  • Components retained between campaigns.
  • Components disposed after each batch, campaign, or product.
  • Product-contact status following an integrity failure.
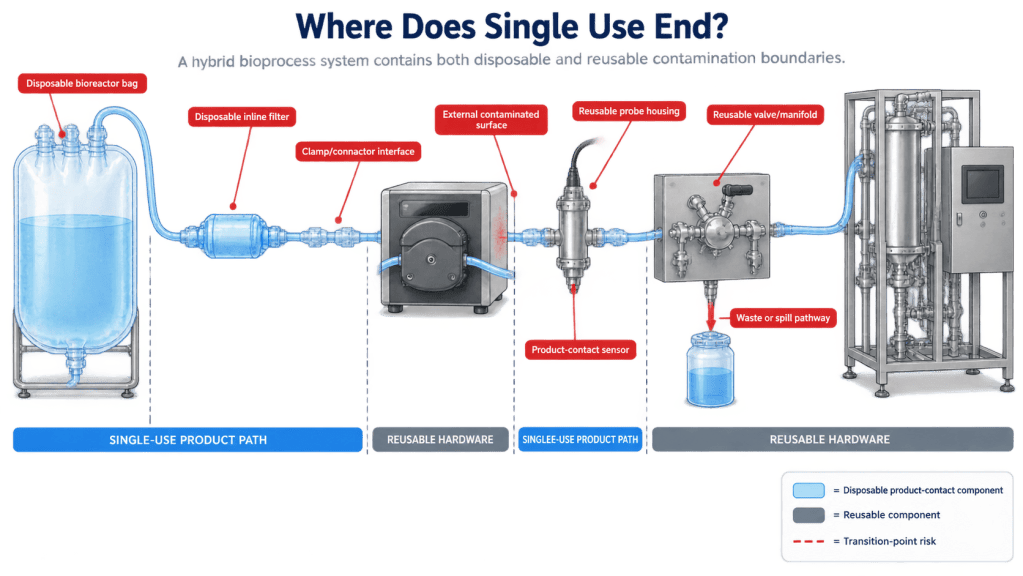
Hybrid bioprocess flow showing disposable bioreactor bags, tubing, filters, and connectors transitioning to reusable pump, sensor, transfer-panel, and chromatography hardware; red callouts mark contamination-control boundaries and spill pathways.

Integrity as contamination control

SUS integrity is both a sterility issue and a cross-contamination issue. A leak can release product into the room, contaminate equipment exteriors, expose operators, or create a pathway into another process. A loss of integrity may also allow environmental or adjacent-process contamination into the system.

Annex 1 expects SUS to maintain integrity under intended processing conditions and identifies extreme operations, including freezing, thawing, transport, and manipulation, as relevant challenges. Qualification should therefore address worst-case pressure, vacuum, agitation, temperature, duration, shipping, installation, connection, and operator handling, not merely supplier burst-test data.

Controls should include:

  • Qualified component and assembly suppliers.
  • Defined critical quality attributes and specifications.
  • Verification of sterilization evidence for each received unit where applicable.
  • Incoming inspection and packaging-integrity checks.
  • Controlled storage and handling.
  • Installation and connection instructions designed to prevent error.
  • Pre-use and, where justified, post-use integrity testing.
  • Leak response and contamination-boundary assessment.
  • Weld and connector qualification.
  • Operator qualification for assembly and manipulation.
  • Supplier change notification and comparability assessment.

Extractables and leachables

SUS removes one patient-safety concern, previous-product residue from reused contact surfaces, but introduces another: chemical species migrating from polymeric components. Annex 1 requires evaluation of product adsorption and reactivity under process conditions and assessment of extractable and leachable profiles, particularly for high-risk components, long contact times, or materials capable of absorbing process constituents.

The evaluation should consider the full process, including sterilization method and dose, contact time, temperature, pH, solvent characteristics, surface-area-to-volume ratio, agitation, storage, freezing and thawing, and cumulative contact across assemblies. Supplier extractables packages are inputs, not automatic proof of suitability. Their test conditions must be scientifically bridged to the actual process.

This is another point at which human safety expertise matters. A detected or predicted leachable should be evaluated against an appropriate toxicological threshold and clinical exposure scenario. The product-safety assessment for a multi-product facility therefore has two related but distinct jobs: establishing safe exposure to previous-product residues and evaluating patient exposure to process-material leachables.

Mix-up risk

SUS can reduce cleaning-related carryover while increasing configuration and mix-up risk. Multi-product facilities may hold visually similar bags, manifolds, filters, connectors, and tubing sets for several clients. A correct component assembled in the wrong orientation, or a wrong component with a compatible connection, can defeat the process while looking superficially acceptable.

Controls should include unique part numbers, electronic bill-of-material verification, barcode or equivalent identification, kitting, line clearance, independent verification of critical assemblies, connection maps, recipe interlocks where possible, and reconciliation of issued, used, and discarded components.

Facility and Process Controls

Equipment choice is only one layer. The facility must prevent contamination through the broader manufacturing environment.

EU GMP Chapter 5 identifies technical and organizational measures that may include dedicated premises or equipment, self-contained areas, closed systems, local extraction, pressure cascades, transfer controls, validated cleaning, waste management, protective clothing, campaign manufacture, and verification of control effectiveness. WHO similarly emphasizes technical and organizational controls, closed systems, cleaning validation, dedicated areas or equipment where justified, and periodic review of cross-contamination measures.

A hierarchy of controls is useful:

  1. Eliminate the pathway: Exclude an incompatible product, avoid open handling, or remove shared product contact.
  2. Physically contain or segregate: Use closed processing, dedicated suites, separate HVAC, barriers, isolators, or dedicated equipment.
  3. Engineer the interface: Use contained transfer, validated connectors, local extraction, pressure control, automation, and interlocks.
  4. Validate removal or inactivation: Apply reproducible cleaning and decontamination with adequate analytical verification.
  5. Control organization and sequence: Campaign, schedule, restrict personnel movement, segregate tools and materials, and perform line clearance.
  6. Detect loss of control: Use environmental, surface, residue, process, and maintenance monitoring targeted to credible failure modes.

Procedures and training are essential, but they are weaker than elimination, containment, and engineering controls. A risk assessment that accepts a high-consequence pathway because “operators are trained” is usually signaling that stronger controls were not seriously considered.

Campaigning

Campaign manufacture separates products in time, not space. It can reduce simultaneous exposure but does not remove residues already present in equipment, rooms, utilities, or shared support areas. Campaigning is acceptable only when paired with a validated and operationally controlled changeover capable of restoring the facility to the required state.

The campaign assessment should consider maximum campaign length, residue accumulation, microbial control, resin or membrane reuse, room and equipment cleaning, environmental persistence, maintenance during the campaign, and the likelihood that repeated setup creates normalized deviations.

Dedicated equipment

Dedication should be based on patient risk and control capability, not convention alone. Packed chromatography resins, membranes, or other retained components may be product-dedicated when they are difficult to clean, cannot be sampled representatively, retain product, or create unacceptable uncertainty. But a universal rule that every column or membrane must be dedicated is not a substitute for assessment.

Conversely, a low calculated carryover limit should not be used to justify sharing when the equipment cannot be cleaned, sampled, or verified with adequate margin. The decision to share requires alignment among toxicological acceptability, technical capability, analytical capability, and operational reliability.

Biological Hazards Beyond Product Residue

A cross-contamination assessment cannot stop at active-protein carryover. The process may contain host cells, cell-culture components, host-cell proteins, DNA, viruses or virus-like particles, mycoplasma, bacteria, fungi, endotoxin, cleaning agents, process additives, and product variants.

ICH Q5A(R2) describes three complementary viral-safety controls for biotechnology products: selection and testing of cell lines and raw materials, demonstration of process clearance for adventitious and endogenous viruses, and testing at appropriate production stages. These controls do not replace facility cross-contamination controls. They address product viral safety, while the facility assessment must also prevent pre-clearance material, cell-culture fluids, or laboratory challenge material from crossing into post-clearance or unrelated operations.

The assessment should distinguish at least:

  • Pre-viral-clearance from post-viral-clearance operations.
  • Live-cell or harvest operations from purified-product operations.
  • Product-specific residue from nonspecific organic residue.
  • Microbial contamination from adventitious viral contamination.
  • Endotoxin from viable organisms.
  • Process organisms from environmental organisms.
  • Laboratory viral-clearance studies from manufacturing operations.

Environmental monitoring can support control of viable and particulate contamination, but it is generally not the primary method for detecting product-to-productcarryover. Product-residue pathways require appropriately specific surface, rinse, process, or investigative methods. The monitoring strategy must match the contaminant and pathway.

Analytical Strategy

Analytical capability should be designed from the risk question, not selected because a platform method is already available.

For reusable equipment, the method must detect the residue or a justified surrogate at a level below the operational acceptance criterion, in the presence of cleaning agents, degradants, surface effects, and sampling losses. FDA expects evaluation of both method sensitivity and the ability of the sampling procedure to recover contamination from equipment surfaces.

Possible approaches include:

  • Product-specific immunoassays.
  • Total organic carbon where scientifically justified as a nonspecific measure.
  • HPLC or UPLC methods.
  • Mass spectrometric peptide or protein methods.
  • Protein assays, conductivity, or other process-specific techniques when sufficiently sensitive and selective.
  • PCR or sequencing for defined nucleic-acid or adventitious-agent questions.
  • Microbial and endotoxin methods for relevant biological residues.

The analytical target profile should define intended use, analyte, matrix, required sensitivity, specificity, reportable range, precision, recovery, robustness, and decision threshold. For a CDMO platform, the strategy should explain when a platform method is acceptable, when a product-specific method is required, and how bridging will be performed.

Method capability should influence the manufacturing decision. If the safe carryover level is below what can be reliably sampled and measured, the answer is not to accept the analytical gap. The control strategy must change: through dedication, disposal, additional segregation, improved cleaning, a more sensitive method, or exclusion of the product from the facility.

Control Strength, Not Control Count

A long list of controls can create the illusion of safety. Ten weak, dependent controls are not equivalent to two strong, independent controls.

LOPA is useful here because it asks whether a protection layer is specific, independent, dependable, and auditable. For example, an operator verifying a hose connection and a second operator checking the same connection may be useful, but both controls depend on the same labeling, work environment, and human interpretation. They are not necessarily independent layers.

A stronger scenario might combine:

  • Physically incompatible connectors.
  • Electronic component verification.
  • Recipe interlock.
  • Independent line-clearance verification.
  • Post-assembly integrity testing.

The assessment should document not only that a control exists but also:

  • What failure it prevents or detects.
  • Whether it is preventive or detective.
  • Whether it is independent of other controls.
  • How its effectiveness was established.
  • What evidence demonstrates continued performance.
  • What happens when it fails.

Regulatory inspection guidance for shared facilities similarly emphasizes documenting the process train and controls in enough detail to identify failure opportunities rather than assuming controls are effective.

Make the Risk Assessment Operational

A risk assessment should change how the facility operates. If it does not affect design, scheduling, qualification, training, monitoring, or release, it is probably only a document.

The output should establish:

  • Whether the product is acceptable for the facility.
  • Permitted suites, equipment trains, and scales.
  • Reusable, disposable, and dedicated boundaries.
  • Required campaign sequence and changeover.
  • Cleaning and decontamination requirements.
  • Product-specific analytical requirements.
  • Personnel and material-flow restrictions.
  • Environmental or surface-monitoring requirements.
  • Required engineering modifications.
  • Conditions that prohibit concurrent manufacture.
  • Required controls for maintenance and intervention.
  • Residual risks and formal acceptance authority.
  • Triggers for reassessment.

The decision should be made by a cross-functional team with authority and expertise in toxicology or pharmacology, quality assurance, manufacturing, MSAT, engineering, validation, microbiology, analytical science, EHS or industrial hygiene, supply chain, and the client’s product knowledge. Commercial stakeholders may contribute constraints and timing, but they should not define the patient-safety threshold.

Lifecycle Governance

The assessment cannot be frozen at technology transfer. ICH Q9(R1) includes risk review as an explicit element of QRM, and EMA expects periodic reassessment of the pharmacological and toxicological basis of HBELs.

Reassessment triggers should include:

  • New clinical or nonclinical safety information.
  • Change in dose, route, indication, or patient population.
  • New product introduction or changed manufacturing sequence.
  • Scale, batch-size, or equipment-train change.
  • Change from reusable to single-use equipment or the reverse.
  • New SUS component, material, supplier, sterilization process, or assembly design.
  • Cleaning-agent, cycle, recipe, or analytical-method change.
  • Facility, HVAC, pressure, flow, or room-use change.
  • Repeated cleaning deviations or adverse process-capability trends.
  • Integrity failures, leaks, or recurring connection errors.
  • Maintenance findings affecting cleanability or containment.
  • New organism or adventitious-agent information.
  • Regulatory change or inspection commitment.

A facility-level product matrix should remain under controlled ownership and identify, for every product, its HBEL status, hazard characteristics, applicable equipment, cleaning family, analytical method, dedication requirements, incompatibilities, and approval status. The matrix should not become an uncontrolled scheduling aid; it is a lifecycle quality record.

What Good Looks Like

A mature CDMO can answer the following questions without assembling a crisis team:

  • Which qualified expert established the HBEL, from what data, and when was it last reviewed?
  • What critical effect drives the limit, and how does uncertainty affect the control strategy?
  • Which product pair creates the most stringent carryover condition on each shared train?
  • Where exactly are the reusable and disposable boundaries?
  • Which SUS components carry the greatest integrity or leachables risk?
  • What contamination pathways remain if the first control fails?
  • Which controls are genuinely independent?
  • Can the cleaning process repeatedly achieve the required limit with margin?
  • Can the sampling and analytical methods detect failure at the required level?
  • What happens after a leak, torn bag, failed connector, maintenance intervention, or incomplete line clearance?
  • Which new information automatically reopens the assessment?

If those answers exist only in separate toxicology reports, validation protocols, supplier files, and local SOPs, the organization does not yet have an integrated cross-contamination control strategy. It has fragments.

The Hard Decision

The purpose of risk assessment is not to prove that every product can fit into the facility. Sometimes the scientifically correct conclusion is that it cannot.

A product may require dedicated equipment, a dedicated suite, a fully disposable flow path, additional containment, a different manufacturing sequence, or exclusion from the site because:

  • The HBEL is extremely low or cannot be established with adequate confidence.
  • The hazard includes sensitization, genotoxicity, potent immune activity, or another effect poorly controlled by ordinary cleaning assumptions.
  • The safe residue level is below analytical or sampling capability.
  • The molecule is not reliably removed or inactivated.
  • The process requires open handling that creates an uncontrolled pathway.
  • The facility cannot segregate pre- and post-clearance activities adequately.
  • The SUS boundary contains unacceptable reusable interfaces.
  • The organization cannot demonstrate control after foreseeable human or mechanical failure.

That decision is not evidence that the risk-management process failed. It is evidence that the process worked.

A Better Synthesis

Reusable equipment and single-use systems should not be treated as competing philosophies. They are different control architectures.

Reusable equipment concentrates the burden on cleanable design, validated removal, analytical evidence, maintenance, and disciplined changeover. Single-use systems reduce some direct carryover pathways but concentrate the burden on system boundaries, integrity, supplier oversight, sterilization assurance, material compatibility, extractables and leachables, configuration control, and human assembly.

The human product-safety assessment sits upstream of both. It defines the exposure boundary that gives every downstream control meaning. Without it, cleaning limits are arbitrary, dedication decisions are conventional, and facility-fit conclusions are little more than confidence statements.

For a multi-product CDMO, the strongest contamination control strategy is therefore not the one with the most controls or the greatest use of disposable technology. It is the one that can connect, without gaps:

patient hazard → safe exposure → contamination pathway → equipment boundary → control mechanism → verification evidence → lifecycle review.

That chain is the real product of the risk assessment. Everything else is documentation supporting it.
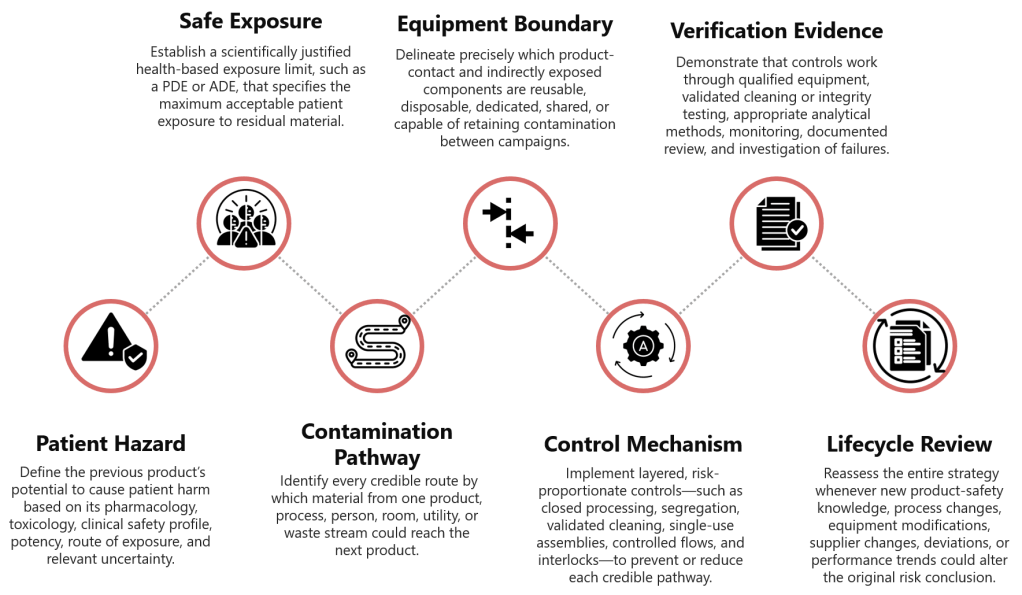

even-step contamination-control framework linking patient hazard to safe exposure, contamination pathways, equipment boundaries, control mechanisms, verification evidence, and lifecycle review for ongoing cross-contamination risk management.

The Product Lifecycle Management Document: Pharmaceutical Quality’s Central Repository for Managing Post-Approval Reality

Pharmaceutical regulatory frameworks have evolved substantially over the past two decades, moving from fixed-approval models—where products remained frozen in approved specifications after authorization—toward dynamic lifecycle management approaches that acknowledge manufacturing reality. Products don’t remain static across their commercial life. Manufacturing sites scale up. Suppliers introduce new materials. Analytical technologies improve. Equipment upgrades occur. Process understanding deepens through continued manufacturing experience. Managing these inevitable changes while maintaining product quality and regulatory compliance has historically required regulatory submission and approval for nearly every meaningful post-approval modification, regardless of risk magnitude or scientific foundation.

This traditional submission-for-approval model reflected regulatory frameworks designed when pharmaceutical manufacturing was less understood, analytical capabilities were more limited, and standardized post-approval change procedures were the best available mechanism for regulatory oversight. Organizations would develop products, conduct manufacturing validation, obtain market approval, then essentially operate within a frozen state of approval—any meaningful change required regulatory notification and frequently required prior approval before distribution of product made under the changed conditions.

The limitations of this approach became increasingly apparent over the 2000s. Regulatory approval cycles extended as the volume of submitted changes increased. Organizations deferred beneficial improvements to avoid submission burden. Supply chain disruptions couldn’t be addressed quickly because qualified alternative suppliers required prior approval supplements with multi-year review timelines. Manufacturing facilities accumulated technical debt—aging equipment, suboptimal processes, outdated analytical methods—because upgrading would trigger regulatory requirements disproportionate to the quality impact. Quality culture inadvertently incentivized resistance to change rather than continuous improvement.

Simultaneously, the pharmaceutical industry’s scientific understanding evolved. Quality by Design (QbD) principles, implemented through ICH Q8 guidance on pharmaceutical development, enabled organizations to develop products with comprehensive process understanding and characterized design spaces. ICH Q10 on pharmaceutical quality systems introduced systematic approaches to knowledge management and continual improvement. Risk management frameworks (ICH Q9) provided scientific methods to evaluate change impact with quantitative rigor. This growing scientific sophistication created opportunity for more nuanced, risk-informed post-approval change management than the binary approval/no approval model permitted.

ICH Q12 “Technical and Regulatory Considerations for Pharmaceutical Product Lifecycle Management” represents the evolution toward scientific, risk-based lifecycle management frameworks. Rather than treating all post-approval changes as equivalent regulatory events, Q12 provides a comprehensive toolbox: Established Conditions (designating which product elements warrant regulatory oversight if changed), Post-Approval Change Management Protocols (enabling prospective agreement on how anticipated changes will be implemented), categorized reporting approaches (aligning regulatory oversight intensity with quality risk), and the Product Lifecycle Management (PLCM) document as central repository for this lifecycle strategy.

The PLCM document itself represents this evolutionary mindset. Where traditional regulatory submissions distribute CMC information across dozens of sections following Common Technical Document structure, the PLCM document consolidates lifecycle management strategy into a central location accessible to regulatory assessors, inspectors, and internal quality teams. The document serves “as a central repository in the marketing authorization application for Established Conditions and reporting categories for making changes to Established Conditions”. It outlines “the specific plan for product lifecycle management that includes the Established Conditions, reporting categories for changes to Established Conditions, PACMPs (if used), and any post-approval CMC commitments”.

This approach doesn’t abandon regulatory oversight. Rather, it modernizes oversight mechanisms by aligning regulatory scrutiny with scientific understanding and risk assessment. High-risk changes warrant prior approval. Moderate-risk changes warrant notification to maintain regulators’ awareness. Low-risk changes can be managed through pharmaceutical quality systems without regulatory notification—though the robust quality system remains subject to regulatory inspection.

The shift from fixed-approval to lifecycle management represents maturation in how the pharmaceutical industry approaches quality. Instead of assuming that quality emerges from regulatory permission, the evolved approach recognizes that quality emerges from robust understanding, effective control systems, and systematic continuous improvement. Regulatory frameworks support this quality assurance by maintaining oversight appropriate to risk, enabling efficient improvement implementation, and incentivizing investment in product and process understanding that justifies flexibility.

For pharmaceutical organizations, this evolution creates both opportunity and complexity. The opportunity is substantial: post-approval flexibility enabling faster response to supply chain challenges, incentives for continuous improvement no longer penalized by submission burden, manufacturing innovation supported by risk-based change management rather than constrained by regulatory caution. The complexity emerges from requirements to build the organizational capability, scientific understanding, and quality system infrastructure supporting this more sophisticated approach.

The PLCM document is the central planning and communication tool, making this evolution operational. Understanding what PLCM documents are, how they’re constructed, and how they connect control strategy development to commercial lifecycle management is essential for organizations navigating this transition from fixed-approval models toward dynamic, evidence-based lifecycle management.

Established Conditions: The Foundation Underlying PLCM Documents

The PLCM document cannot be understood without first understanding Established Conditions—the regulatory construct that forms the foundation for modern lifecycle management approaches. Established Conditions (ECs) are elements in a marketing application considered necessary to assure product quality and therefore requiring regulatory submission if changed post-approval. This definition appears straightforward until you confront the judgment required to distinguish “necessary to assure product quality” from the extensive supporting information submitted in regulatory applications that doesn’t meet this threshold.

The pharmaceutical development process generates enormous volumes of data. Formulation screening studies. Process characterization experiments. Analytical method development. Stability studies. Scale-up campaigns. Manufacturing experience from clinical trial material production. Much of this information appears in regulatory submissions because it supports and justifies the proposed commercial manufacturing process and control strategy. But not all submitted information constitutes an Established Condition.

Consider a monoclonal antibody purification process submitted in a biologics license application. The application describes the chromatography sequence: Protein A capture, viral inactivation, anion exchange polish, cation exchange polish. For each step, the application provides:

  • Column resin identity and supplier
  • Column dimensions and bed height
  • Load volume and load density
  • Buffer compositions and pH
  • Flow rates
  • Gradient profiles
  • Pool collection criteria
  • Development studies showing how these parameters were selected
  • Process characterization data demonstrating parameter ranges that maintain product quality
  • Viral clearance validation demonstrating step effectiveness

Which elements are Established Conditions requiring regulatory submission if changed? Which are supportive information that can be managed through the Pharmaceutical Quality System without regulatory notification?

The traditional regulatory approach made everything potentially an EC through conservative interpretation—any element described in the application might require submission if changed. This created perverse incentives against thorough process description (more detail creates more constraints) and against continuous improvement (changes trigger submission burden regardless of quality impact). ICH Q12 explicitly addresses this problem by distinguishing ECs from supportive information and providing frameworks for identifying ECs based on product and process understanding, quality risk management, and control strategy design.

The guideline describes three approaches to identifying process parameters as ECs:

Minimal parameter-based approach: Critical process parameters (CPPs) and other parameters where impact on product quality cannot be reasonably excluded are identified as ECs. This represents the default position requiring limited process understanding—if you haven’t demonstrated that a parameter doesn’t impact quality, assume it’s critical and designate it an EC. For our chromatography example, this approach would designate most process parameters as ECs: resin type, column dimensions, load parameters, buffer compositions, flow rates, gradient profiles. Only clearly non-impactful variables (e.g., specific pump model, tubing lengths within reasonable ranges) would be excluded.

Enhanced parameter-based approach: Leveraging extensive process characterization and understanding of parameter impacts on Critical Quality Attributes (CQAs), the organization identifies which parameters are truly critical versus those demonstrated to have minimal quality impact across realistic operational ranges. Process characterization studies using Design of Experiments (DoE), prior knowledge from similar products, and mechanistic understanding support justifications that certain parameters, while described in the application for completeness, need not be ECs because quality impact has been demonstrated to be negligible. For our chromatography process, enhanced understanding might demonstrate that precise column dimensions matter less than maintaining appropriate bed height and superficial velocity within characterized ranges. Gradient slope variations within defined design space don’t impact product quality measurably. Flow rate variations of ±20% from nominal don’t affect separation performance meaningfully when other parameters compensate appropriately.

Performance-based approach: Rather than designating input parameters (process settings) as ECs, this approach designates output performance criteria—in-process or release specifications that assure quality regardless of how specific parameters vary. For chromatography, this might mean the EC is aggregate purity specification rather than specific column operating parameters. As long as the purification process delivers aggregates below specification limits, variation in how that outcome is achieved doesn’t require regulatory notification. This provides maximum flexibility but requires robust process understanding, appropriate performance specifications representing quality assurance, and effective pharmaceutical quality system controls.

The choice among these approaches depends on product and process understanding available at approval and organizational lifecycle management strategy. Products developed with minimal Quality by Design (QbD) application, limited process characterization, and traditional “recipe-based” approaches default toward minimal parameter-based EC identification—describing most elements as ECs because insufficient knowledge exists to justify alternatives. Products developed with extensive QbD, comprehensive process characterization, and demonstrated design spaces can justify enhanced or performance-based approaches that provide greater post-approval flexibility.

This creates strategic implications. Organizations implementing ICH Q12 for legacy products often confront applications describing processes in detail without the underlying characterization studies that would support enhanced EC approaches. The submitted information implies everything might be critical because nothing was systematically demonstrated non-critical. Retrofitting ICH Q12 concepts requires either accepting conservative EC designation (reducing post-approval flexibility) or conducting characterization studies to generate understanding supporting more nuanced EC identification. The latter option represents significant investment but potentially generates long-term value through reduced regulatory submission burden for routine lifecycle changes.

For new products, the strategic decision occurs during pharmaceutical development. QbD implementation, process characterization investment, and design space establishment aren’t simply about demonstrating understanding to reviewers—they create the foundation for efficient lifecycle management by enabling justified EC identification that balances quality assurance with operational flexibility.

The PLCM Document Structure: Central Repository for Lifecycle Strategy

The PLCM document consolidates this EC identification and associated lifecycle management planning into a central location within the regulatory application. ICH Q12 describes the PLCM document as serving “as a central repository in the marketing authorization application for ECs and reporting categories for making changes to ECs”. The document “outlines the specific plan for product lifecycle management that includes the ECs, reporting categories for changes to ECs, PACMPs (if used) and any post-approval CMC commitments”.

The functional purpose is transparency and predictability. Regulatory assessors reviewing a marketing application can locate the PLCM document and immediately understand:

  • Which elements the applicant considers Established Conditions (versus supportive information)
  • The reporting category the applicant believes appropriate if each EC changes (prior approval, notification, or managed solely in PQS)
  • Any Post-Approval Change Management Protocols (PACMPs) proposed for planned future changes
  • Specific post-approval CMC commitments made during regulatory negotiations

This consolidation addresses a persistent challenge in regulatory assessment and inspection. Traditional applications distribute CMC information across dozens of sections following Common Technical Document (CTD) structure. Critical process parameters appear in section 3.2.S.2.2 or 3.2.P.3.3. Specifications appear in 3.2.S.4.1 or 3.2.P.5.1. Analytical procedures scatter across multiple sections. Control strategy discussions appear in pharmaceutical development sections. Regulatory commitments might exist in scattered communications, meeting minutes, and approval letters accumulated over the years.

When post-approval changes arise, determining what requires submission involves archeology through historical submissions, approval letters, and regional regulatory guidance. Different regional regulatory authorities might interpret submission requirements differently. Change control groups debate whether manufacturing site changes to mixing speed from 150 RPM to 180 RPM triggers prior approval (if RPM was specified in the approved application) or represent routine optimization (if only “appropriate mixing” was specified).

The PLCM document centralizes this information and makes commitments explicit. When properly constructed and maintained, the PLCM becomes the primary reference for change management decisions and regulatory inspection discussions about lifecycle management approach.

Core Elements of the PLCM Document

ICH Q12 specifies that the PLCM document should contain several key elements:

Summary of product control strategy: A high-level summary clarifying and highlighting which control strategy elements should be considered ECs versus supportive information. This summary addresses the fundamental challenge that control strategies contain extensive elements—material controls, in-process testing, process parameter monitoring, release testing, environmental monitoring, equipment qualification requirements, cleaning validation—but not all control strategy elements necessarily rise to EC status requiring regulatory submission if changed. The control strategy summary in the PLCM document maps this landscape, distinguishing legally binding commitments from quality system controls.

Established Conditions listing: The proposed ECs for the product should be listed comprehensively with references to detailed information located elsewhere in the CTD/eCTD structure. A tabular format is recommended though not mandatory. The table typically includes columns for: CTD section reference, EC description, justification for EC designation, current approved state, and reporting category for changes.

Reporting category assignments: For each EC, the reporting category indicates whether changes require prior approval (major changes with high quality risk), notification to regulatory authority (moderate changes with manageable risk), or can be managed solely within the PQS without regulatory notification (minimal or no quality risk). These categorizations should align with regional regulatory frameworks (21 CFR 314.70 in the US, EU variation regulations, equivalent frameworks in other ICH regions) while potentially proposing justified deviations based on product-specific risk assessment.

Post-Approval Change Management Protocols: If the applicant has developed PACMPs for anticipated future changes, these should be referenced in the PLCM document with location of the detailed protocols elsewhere in the submission. PACMPs represent prospective agreements with regulatory authorities about how specific types of changes will be implemented, what studies will support implementation, and what reporting category will apply when acceptance criteria are met. The PLCM document provides the index to these protocols.

Post-approval CMC commitments: Any commitments made to regulatory authorities during assessment—additional validation studies, monitoring programs, method improvements, process optimization plans—should be documented in the PLCM with timelines and expected completion. This addresses the common problem of commitments made during approval negotiations becoming lost or forgotten without systematic tracking.

The document is submitted initially with the marketing authorization application or via supplement/variation for marketed products when defining ECs. Following approval, the PLCM document should be updated in post-approval submissions for CMC changes, capturing how ECs have evolved and whether commitments have been fulfilled.

Location and Format Within Regulatory Submissions

The PLCM document can be located in eCTD Module 1 (regional administrative information), Module 2 (summaries), or Module 3 (quality information) based on regional regulatory preferences. The flexibility in location reflects that the PLCM document functions somewhat differently than traditional CTD sections—it’s a cross-reference and planning document rather than detailed technical information.

Module 3 placement (likely section 3.2.P.2 or 3.2.S.2 as part of pharmaceutical development discussions) positions the PLCM document alongside control strategy descriptions and process development narratives. This co-location makes logical sense—the PLCM represents the regulatory management strategy for the control strategy and process described in those sections.

Module 2 placement (within quality overall summary sections) positions the PLCM as summary-level strategic document, which aligns with its function as a high-level map rather than detailed specification.

Module 1 placement reflects that the PLCM document contains primarily regulatory process information (reporting categories, commitments) rather than scientific/technical content.

In practice, consultation with regional regulatory authorities during development or pre-approval meetings can clarify preferred location. The critical requirement is consistency and findability—inspectors and assessors need to locate the PLCM document readily.

The tabular format recommended for key PLCM elements facilitates comprehension and maintenance. ICH Q12 Annex IF provides an illustrative example showing how ECs, reporting categories, justifications, PACMPs, and commitments might be organized in tabular structure. While this example shouldn’t be treated as prescriptive template, it demonstrates organizational principles: grouping by product attribute (drug substance vs. drug product), clustering related parameters, referencing detailed justifications in development sections rather than duplicating extensive text in the table.

Control Strategy: The Foundation From Which ECs Emerge

The PLCM document’s Established Conditions emerge from the control strategy developed during pharmaceutical development and refined through technology transfer and commercial manufacturing experience. Understanding how PLCM documents relate to control strategy requires understanding what control strategies are, how they evolve across the lifecycle, and which control strategy elements become ECs versus remaining internal quality system controls.

ICH Q10 defines control strategy as “a planned set of controls, derived from current product and process understanding, that assures process performance and product quality”. This deceptively simple definition encompasses extensive complexity. The “planned set of controls” includes multiple layers:

  • Controls on material attributes: Specifications and acceptance criteria for starting materials, excipients, drug substance, intermediates, and packaging components. These controls ensure incoming materials possess the attributes necessary for the manufacturing process to perform as designed and the final product to meet quality standards.
  • Controls on the manufacturing process: Process parameter ranges, operating conditions, sequence of operations, and in-process controls that govern how materials are transformed into drug product. These include both parameters that operators actively control (temperatures, pressures, mixing speeds, flow rates) and parameters that are monitored to verify process state (pH, conductivity, particle counts).
  • Controls on drug substance and drug product: Release specifications, stability monitoring programs, and testing strategies that verify the final product meets all quality requirements before distribution and maintains quality throughout its shelf life.
  • Controls implicit in process design: Elements like sequence of unit operations, order of addition, purification step selection that aren’t necessarily “controlled” in real-time but represent design decisions that assure quality. A viral inactivation step positioned after affinity chromatography but before polishing steps exemplifies implicit control—the sequence matters for process performance but isn’t a parameter operators adjust batch-to-batch.
  • Environmental and facility controls: Clean room classifications, environmental monitoring programs, utilities qualification, equipment maintenance, and calibration that create the context within which manufacturing occurs.

The control strategy is not a single document. It’s distributed across process descriptions, specifications, SOPs, batch records, validation protocols, equipment qualification protocols, environmental monitoring programs, stability protocols, and analytical methods. What makes these disparate elements a “strategy” is that they collectively and systematically address how Critical Quality Attributes are ensured within appropriate limits throughout manufacturing and shelf life.

Control Strategy Development During Pharmaceutical Development

Control strategies don’t emerge fully formed at the end of development. They evolve systematically as product and process understanding grows.

Early development focuses on identifying what quality attributes matter. The Quality Target Product Profile (QTPP) articulates intended product performance, dosage form, route of administration, strength, stability, and quality characteristics necessary for safety and efficacy. From QTPP, potential Critical Quality Attributes are identified—the physical, chemical, biological, or microbiological properties that should be controlled within appropriate limits to ensure product quality.

For a monoclonal antibody therapeutic, potential CQAs might include: protein concentration, high molecular weight species (aggregates), low molecular weight species (fragments), charge variants, glycosylation profile, host cell protein levels, host cell DNA levels, viral safety, endotoxin levels, sterility, particulates, container closure integrity. Not all initially identified quality attributes prove critical upon investigation, but systematic evaluation determines which attributes genuinely impact safety or efficacy versus which can vary without meaningful consequence.

Risk assessment identifies which formulation components and process steps might impact these CQAs. For attributes confirmed as critical, development studies characterize how material attributes and process parameters affect CQA levels. Design of Experiments (DoE), mechanistic models, scale-down models, and small-scale studies explore parameter space systematically.

This characterization reveals Critical Material Attributes (CMAs)—characteristics of input materials that impact CQAs when varied—and Critical Process Parameters (CPPs)—process variables that affect CQAs. For our monoclonal antibody, CMAs might include cell culture media glucose concentration (affects productivity and glycosylation), excipient sources (affect aggregation propensity), and buffer pH (affects stability). CPPs might include bioreactor temperature, pH control strategy, harvest timing, chromatography load density, viral inactivation pH and duration, ultrafiltration/diafiltration concentration factors.

The control strategy emerges from this understanding. CMAs become specifications on incoming materials. CPPs become controlled process parameters with defined operating ranges in batch records. CQAs become specifications with appropriate acceptance criteria. Process analytical technology (PAT) or in-process testing provides real-time verification that process state aligns with expectations. Design spaces, when established, define multidimensional regions where input variables and process parameters consistently deliver quality.

Control Strategy Evolution Through Technology Transfer and Commercial Manufacturing

The control strategy at approval represents best understanding achieved during development and clinical manufacturing. Technology transfer to commercial manufacturing sites tests whether that understanding transfers successfully—whether commercial-scale equipment, commercial facility environments, and commercial material sourcing produce equivalent product quality when operating within the established control strategy.

Technology transfer frequently reveals knowledge gaps. Small-scale bioreactors used for clinical supply might achieve adequate oxygen transfer through simple impeller agitation; commercial-scale 20,000L bioreactors require sparging strategy design considering bubble size, gas flow rates, and pressure control that weren’t critical at smaller scale. Heat transfer dynamics differ between 200L and 2000L vessels, affecting cooling/heating rates and potentially impacting CQAs sensitive to temperature excursions. Column packing procedures validated on 10cm diameter columns at development scale might not translate directly to 80cm diameter columns at commercial scale.

These discoveries during scale-up, process validation, and early commercial manufacturing build on development knowledge. Process characterization at commercial scale, continued process verification, and manufacturing experience over initial production batches refine understanding of which parameters truly drive quality versus which development-scale sensitivities don’t manifest at commercial scale.

The control strategy should evolve to reflect this learning. Parameters initially controlled tightly based on limited understanding might be relaxed when commercial experience demonstrates wider ranges maintain quality. Parameters not initially recognized as critical might be added when commercial-scale phenomena emerge. In-process testing strategies might shift from extensive sampling to targeted critical points when process capability is demonstrated.

ICH Q10 explicitly envisions this evolution, describing pharmaceutical quality system objectives that include “establishing and maintaining a state of control” and “facilitating continual improvement”. The state of control isn’t static—it’s dynamic equilibrium where process understanding, monitoring, and control mechanisms maintain product quality while enabling adaptation as knowledge grows.

Connecting Control Strategy to PLCM Document: Which Elements Become Established Conditions?

The control strategy contains far more elements than should be Established Conditions. This is where the conceptual distinction between control strategy (comprehensive quality assurance approach) and Established Conditions (regulatory commitments requiring submission if changed) becomes critical.

Not all controls necessary to assure quality need regulatory approval before changing. Organizations should continuously improve control strategies based on growing knowledge, without regulatory approval creating barriers to enhancement. The challenge is determining which controls are so fundamental to quality assurance that regulatory oversight of changes is appropriate versus which controls can be managed through pharmaceutical quality systems without regulatory involvement.

ICH Q12 guidance indicates that EC designation should consider:

  • Criticality to product quality: Controls directly governing CQAs or CPPs/CMAs with demonstrated impact on CQAs are candidates for EC status. Release specifications for CQAs clearly merit EC designation—changing acceptance criteria for aggregates in a protein therapeutic affects patient safety and product efficacy directly. Similarly, critical process parameters with demonstrated CQA impact warrant EC consideration.
  • Level of quality risk: High-risk controls where inappropriate change could compromise patient safety should be ECs with prior approval reporting category. Moderate-risk controls might be ECs with notification reporting category. Low-risk controls might not need EC designation.
  • Product and process understanding: Greater understanding enables more nuanced EC identification. When extensive characterization demonstrates certain parameters have minimal quality impact, justification exists for excluding them from ECs. Conversely, limited understanding argues for conservative EC designation until further characterization enables refinement.
  • Regulatory expectations and precedent: While ICH Q12 harmonizes approaches, regional regulatory expectations still influence EC identification strategy. Conservative regulators might expect more extensive EC designation; progressive regulators comfortable with risk-based approaches might accept narrower EC scope when justified.

Consider our monoclonal antibody purification process control strategy. The comprehensive control strategy includes:

  • Column resin specifications (purity, dynamic binding capacity, lot-to-lot variability limits)
  • Column packing procedures (compression force, bed height uniformity testing, packing SOPs)
  • Buffer preparation procedures (component specifications, pH verification, bioburden limits)
  • Equipment qualification status (chromatography skid IQ/OQ/PQ, automated systems validation)
  • Process parameters (load density, flow rates, gradient slopes, pool collection criteria)
  • In-process testing (pool purity analysis, viral clearance sample retention)
  • Environmental monitoring in manufacturing suite
  • Operator training qualification
  • Cleaning validation for equipment between campaigns
  • Batch record templates documenting execution
  • Investigation procedures when deviations occur

Which elements become ECs in the PLCM document?

Using enhanced parameter-based approach with substantial process understanding: Resin specifications for critical attributes (dynamic binding capacity range, leachables below limits) likely merit EC designation—changing resin characteristics affects purification performance and CQA delivery. Load density ranges and pool collection criteria based on specific quality specifications probably merit EC status given their direct connection to product purity and yield. Critical buffer component specifications affecting pH and conductivity (which impact protein behavior on resins) warrant EC consideration.

Buffer preparation SOPs, equipment qualification procedures, environmental monitoring program details, operator training qualification criteria, cleaning validation acceptance criteria, and batch record templates likely don’t require EC designation despite being essential control strategy elements. These controls matter for quality, but changes can be managed through pharmaceutical quality system change control with appropriate impact assessment, validation where needed, and implementation without regulatory notification.

The PLCM document makes these distinctions explicit. The control strategy summary section acknowledges that comprehensive controls exist beyond those designated ECs. The EC listing table specifies which elements are ECs, referencing detailed justifications in development sections. The reporting category column indicates whether EC changes require prior approval (drug substance concentration specification), notification (resin dynamic binding capacity specification range adjustment based on additional characterization), or PQS management only (parameters within approved design space).

How ICH Q12 Tools Integrate Into Overall Lifecycle Management

The PLCM document serves as integrating framework for ICH Q12’s lifecycle management tools: Established Conditions, Post-Approval Change Management Protocols, reporting category assignments, and pharmaceutical quality system enablement.

Post-Approval Change Management Protocols: Planning Future Changes Prospectively

PACMPs address a fundamental lifecycle management challenge: regulatory authorities assess change appropriateness when changes are proposed, but this reactive assessment creates timeline uncertainty and resource inefficiency. Organizations proposing manufacturing site additions, analytical method improvements, or process optimizations submit change supplements, then wait months or years for assessment and approval while maintaining existing less-optimal approaches.

PACMPs flip this dynamic by obtaining prospective agreement on how anticipated changes will be implemented and assessed. The PACMP submitted in the original application or post-approval supplement describes:

  • The change intended for future implementation (e.g., manufacturing site addition, scale-up to larger bioreactors, analytical method improvement)
  • Rationale for the change (capacity expansion, technology improvement, continuous improvement)
  • Studies and validation work that will support change implementation
  • Acceptance criteria that will demonstrate the change maintains product quality
  • Proposed reporting category when acceptance criteria are met

If regulatory authorities approve the PACMP, the organization can implement the described change when studies meet acceptance criteria, reporting results per the agreed category rather than defaulting to conservative prior approval submission. This dramatically improves predictability—the organization knows in advance what studies will suffice and what reporting timeline applies.

For example, a PACMP might propose adding manufacturing capacity at a second site using identical equipment and procedures. The protocol specifies: three engineering runs demonstrating equipment performs comparably; analytical comparability studies showing product quality matches reference site; process performance qualification demonstrating commercial batches meet specifications; stability studies confirming comparable stability profiles. When these acceptance criteria are met, implementation proceeds via notification rather than prior approval supplement.

The PLCM document references approved PACMPs, providing the index to these prospectively planned changes. During regulatory inspections or when implementing changes, the PLCM document directs inspectors and internal change control teams to the relevant protocol describing the agreed implementation approach.

Reporting Categories: Risk-Based Regulatory Oversight

Reporting category assignment represents ICH Q12’s mechanism for aligning regulatory oversight intensity with quality risk. Not all changes merit identical regulatory scrutiny. Changes with high potential patient impact warrant prior approval before implementation. Changes with moderate impact might warrant notification so regulators are aware but don’t need to approve prospectively. Changes with minimal quality risk can be managed through pharmaceutical quality systems without regulatory notification (though inspection verification remains possible).

ICH Q12 encourages risk-based categorization aligned with regional regulatory frameworks while enabling flexibility when justified by product/process understanding and robust PQS. The PLCM document makes categorization explicit and provides justification.

Traditional US framework defines three reporting categories per 21 CFR 314.70:

  • Major changes (prior approval supplement): Changes requiring FDA approval before distribution of product made using the change. Examples include formulation changes affecting bioavailability, new manufacturing sites, significant manufacturing process changes, specification relaxations for CQAs. These changes present high quality risk; regulatory assessment verifies that proposed changes maintain safety and efficacy.
  • Moderate changes (Changes Being Effected or notification): Changes implemented after submission but before FDA approval (CBE-30: 30 days after submission) or notification to FDA without awaiting approval. Examples include analytical method changes, minor formulation adjustments, supplier changes for non-critical materials. Quality risk is manageable; notification ensures regulatory awareness while avoiding unnecessary delay.
  • Minor changes (annual report): Changes reported annually without prior notification. Examples include editorial corrections, equipment replacement with comparable equipment, supplier changes for non-critical non-functional components. Quality risk is minimal; annual aggregation reduces administrative burden while maintaining regulatory visibility.

European variation regulations provide comparable framework with Type IA (notification), Type IB (notification with delayed implementation), and Type II (approval required) variations.

ICH Q12 enables movement beyond default categorization through justified proposals based on product understanding, process characterization, and PQS effectiveness. A change that would traditionally require prior approval might justify notification category when:

  • Extensive process characterization demonstrates the change remains within validated design space
  • Comparability studies show equivalent product quality
  • Robust PQS ensures appropriate impact assessment and validation before implementation
  • PACMP established prospectively agreed acceptance criteria

The PLCM document documents these justified categorizations alongside conservative defaults, creating transparency about lifecycle management approach. When organizations propose that specific EC changes merit notification rather than prior approval based on process understanding, the PLCM provides the location for that proposal and cross-references to supporting justification in development sections.

Pharmaceutical Quality System: The Foundation Enabling Flexibility

None of the ICH Q12 tools—ECs, PACMPs, reporting categories, PLCM documents—function effectively without robust pharmaceutical quality system foundation. The PQS provides the infrastructure ensuring that changes not requiring regulatory notification are nevertheless managed with appropriate rigor.

ICH Q10 describes PQS as the comprehensive framework spanning the entire lifecycle from pharmaceutical development through product discontinuation, with objectives including achieving product realization, establishing and maintaining state of control, and facilitating continual improvement. The PQS elements—process performance monitoring, corrective and preventive action, change management, management review—provide systematic mechanisms for managing all changes (not just those notified to regulators).

When the PLCM document indicates that certain parameters can be adjusted within design space without regulatory notification, the PQS change management system ensures those adjustments undergo appropriate impact assessment, scientific justification, implementation with validation where needed, and effectiveness verification. When parameters are adjusted within specification ranges based on process optimization, CAPA systems ensure changes address identified opportunities while monitoring systems verify maintained quality.

Regulatory inspectors assessing ICH Q12 implementation evaluate PQS effectiveness as much as PLCM document content. An impressive PLCM document with sophisticated EC identification and justified reporting categories means little if the PQS change management system can’t demonstrate appropriate rigor for changes managed internally. Conversely, organizations with robust PQS can justify greater regulatory flexibility because inspectors have confidence that internal management substitutes effectively for regulatory oversight.

The Lifecycle Perspective: PLCM Documents as Living Infrastructure

The PLCM document concept fails if treated as static submission artifact—a form populated during regulatory preparation then filed away after approval. The document’s value emerges from functioning as living infrastructure maintained throughout commercial lifecycle.

Pharmaceutical Development Stage: Establishing Initial PLCM

During pharmaceutical development (ICH Q10’s first lifecycle stage), the focus is designing products and processes that consistently deliver intended performance. Development activities using QbD principles, risk management, and systematic characterization generate the product and process understanding that enables initial control strategy design and EC identification.

At this stage, the PLCM document represents the lifecycle management strategy proposed to regulatory authorities. Development teams compile:

  • Control strategy summary articulating how CQAs will be ensured through material controls, process controls, and testing strategy
  • Proposed EC listing based on available understanding and chosen approach (minimal, enhanced parameter-based, or performance-based)
  • Reporting category proposals justified by development studies and risk assessment
  • Any PACMPs for changes anticipated during commercialization (site additions, scale-up, method improvements)
  • Commitments for post-approval work (additional validation studies, monitoring programs, process characterization to be completed commercially)

The quality of this initial PLCM document depends heavily on development quality. Products developed with minimal process characterization and traditional empirical approaches produce conservative PLCM documents—extensive ECs, default prior approval reporting categories, limited justification for flexibility. Products developed with extensive QbD, comprehensive characterization, and demonstrated design spaces produce strategic PLCM documents—targeted ECs, risk-based reporting categories, justified flexibility.

This creates powerful incentive alignment. QbD investment during development isn’t merely about satisfying reviewers or demonstrating scientific sophistication—it’s infrastructure investment enabling lifecycle flexibility that delivers commercial value through reduced regulatory burden, faster implementation of improvements, and supply chain agility.

Technology Transfer Stage: Testing and Refining PLCM Strategy

Technology transfer represents critical validation of whether development understanding and proposed control strategy transfer successfully to commercial manufacturing. This stage tests the PLCM strategy implicitly—do the identified ECs actually ensure quality at commercial scale? Are proposed reporting categories appropriate for the change types that emerge during scale-up?

Technology transfer frequently reveals refinements needed. Parameters identified as critical at development scale might prove less sensitive commercially due to different equipment characteristics. Parameters not initially critical might require tighter control at larger scale due to heat/mass transfer limitations, longer processing times, or equipment-specific phenomena.

These discoveries should inform PLCM document updates submitted with first commercial manufacturing supplements or variations. The EC listing might be refined based on scale-up learning. Reporting category proposals might be adjusted when commercial-scale validation provides different risk perspectives. PACMPs initially proposed might require modification when commercial manufacturing reveals implementation challenges not apparent from development-scale thinking.

Organizations treating the PLCM as static approval-time artifact miss this refinement opportunity. The PLCM document approved initially reflected best understanding available during development. Commercial manufacturing generates new understanding that should enhance the PLCM, making it more accurate and strategic.

Commercial Manufacturing Stage: Maintaining PLCM as Living Document

Commercial manufacturing represents the longest lifecycle stage, potentially spanning decades. During this period, the PLCM document should evolve continuously as the product evolves.

Post-approval changes occur constantly in pharmaceutical manufacturing. Supplier discontinuations force raw material changes. Equipment obsolescence requires replacement. Analytical methods improve as technology advances. Process optimizations based on manufacturing experience enhance efficiency or robustness. Regulatory standard evolution necessitates updated validation approaches or expanded testing.

Each change potentially affects the PLCM document. If an EC changes, the PLCM document should be updated to reflect the new approved state. If a PACMP is executed and the change implemented, the PLCM should document completion and remove that protocol from active status while adding the implemented change to the EC listing if it becomes a new EC. If post-approval commitments are fulfilled, the PLCM should document completion.

The PLCM document becomes the central change management reference. When change controls propose manufacturing modifications, the first question is: “Does this affect an Established Condition in our PLCM document?” If yes, what’s the reporting category? Do we have an approved PACMP covering this change type? If we’re proposing this change doesn’t require regulatory notification despite affecting described elements, what’s our justification based on design space, process understanding, or risk assessment?

Annual Product Reviews, Management Reviews, and change management metrics should assess PLCM document currency. How many changes implemented last year affected ECs? What reporting categories were used? Were reporting category assignments appropriate retrospectively based on actual quality impact? Are there patterns suggesting EC designation should be refined—parameters initially identified as critical that commercial experience shows have minimal impact, or vice versa?

This dynamic maintenance transforms the PLCM document from regulatory artifact into operational tool for lifecycle management strategy. The document evolves from initial approval state toward increasingly sophisticated representation of how the organization manages quality through knowledge-based, risk-informed change management rather than rigid adherence to initial approval conditions.

Practical Implementation Challenges: PLCM-as-Done Versus PLCM-as-Imagined

The conceptual elegance of PLCM documents—central repository for lifecycle management strategy, transparent communication with regulators, strategic enabler for post-approval flexibility—confronts implementation reality in pharmaceutical organizations struggling with resource constraints, competing priorities, and cultural inertia favoring traditional approaches.

The Knowledge Gap: Insufficient Understanding to Support Enhanced EC Approaches

Many pharmaceutical organizations implementing ICH Q12 confront applications containing limited process characterization. Products approved years or decades ago described manufacturing processes in detail without the underlying DoE studies, mechanistic models, or design space characterization that would support enhanced EC identification.

The submitted information implies everything might be critical because systematic demonstrations of non-criticality don’t exist. Implementing PLCM documents for these legacy products forces uncomfortable choice: designate extensive ECs based on conservative interpretation (accepting reduced post-approval flexibility), or invest in retrospective characterization studies generating understanding needed to justify refined EC identification.

The latter option represents significant resource commitment. Process characterization at commercial scale requires manufacturing capacity allocation, analytical testing resources, statistical expertise for DoE design and interpretation, and time for study execution and assessment. For products with mature commercial manufacturing, this investment competes with new product development, existing product improvements, and operational firefighting.

Organizations often default to conservative EC designation for legacy products, accepting reduced ICH Q12 benefits rather than making characterization investment. This creates two-tier environment: new products developed with QbD approaches achieving ICH Q12 flexibility, while legacy products remain constrained by limited understanding despite being commercially mature.

The strategic question is whether retrospective characterization investment pays back through avoided regulatory submission costs, faster implementation of supply chain changes, and enhanced resilience during material shortages or supplier disruptions. For high-value products with long remaining commercial life, the investment frequently justifies itself. For products approaching patent expiration or with declining volumes, the business case weakens.

The Cultural Gap: Change Management as Compliance Versus Strategic Capability

Traditional pharmaceutical change management culture treats post-approval changes as compliance obligations requiring regulatory permission rather than strategic capabilities enabling continuous improvement. This mindset manifests in change control processes designed to document what changed and ensure regulatory notification rather than optimize change implementation efficiency.

ICH Q12 requires cultural shift from “prove we complied with regulatory notification requirements” toward “optimize lifecycle management strategy balancing quality assurance with operational agility”. This shift challenges embedded assumptions.

The assumption that “more regulatory oversight equals better quality” must confront evidence that excessive regulatory burden can harm quality by preventing necessary improvements, forcing workarounds when optimal changes can’t be implemented due to submission timelines, and creating perverse incentives against process optimization. Quality emerges from robust understanding, effective control, and systematic improvement—not from regulatory permission slips for every adjustment.

The assumption that “regulatory submission requirements are fixed by regulation” must acknowledge that ICH Q12 explicitly encourages justified proposals for risk-based reporting categories differing from traditional defaults. Organizations can propose that specific changes merit notification rather than prior approval based on process understanding, comparability demonstrations, and PQS rigor. But proposing non-default categorization requires confidence to articulate justification and defend during regulatory assessment—confidence many organizations lack.

Building this capability requires training quality professionals, regulatory affairs teams, and change control reviewers in ICH Q12 concepts and their application. It requires developing organizational competency in risk assessment connecting change types to quality impact with quantitative or semi-quantitative justification. It requires quality systems that can demonstrate to inspectors that internally managed changes undergo appropriate rigor even without regulatory oversight.

The Maintenance Gap: PLCM Documents as Static Approval Artifacts Versus Living Systems

Perhaps the largest implementation gap exists between PLCM documents as living lifecycle management infrastructure versus PLCM documents as one-time regulatory submission artifacts. Pharmaceutical organizations excel at generating documentation for regulatory submissions. We struggle with maintaining dynamic documents that evolve with the product.

The PLCM document submitted at approval captures understanding and strategy at that moment. Absent systematic maintenance processes, the document fossilizes. Post-approval changes occur but the PLCM document isn’t updated to reflect current EC state. PACMPs are executed but completion isn’t documented in updated PLCM versions. Commitments are fulfilled but the PLCM document continues listing them as pending.

Within several years, the PLCM document submitted at approval no longer accurately represents current product state or lifecycle management approach. When inspectors request the PLCM document, organizations scramble to reconstruct current state from change control records, approval letters, and variation submissions rather than maintaining the PLCM proactively.

This failure emerges from treating PLCM documents as regulatory submission deliverables (owned by regulatory affairs, prepared for submission, then archived) rather than operational quality system documents (owned by quality systems, maintained continuously, used routinely for change management decisions). The latter requires infrastructure:

  • Document management systems with version control and change history
  • Assignment of PLCM document maintenance responsibility to specific quality system roles
  • Integration of PLCM updates into change control workflows (every approved change affecting ECs triggers PLCM update)
  • Periodic PLCM review during annual product reviews or management reviews to verify currency
  • Training for quality professionals in using PLCM documents as operational references rather than dusty submission artifacts

Organizations implementing ICH Q12 successfully build these infrastructure elements deliberately. They recognize that PLCM document value requires maintenance investment comparable to batch record maintenance, specification maintenance, or validation protocol maintenance—not one-time preparation then neglect.

Strategic Implications: PLCM Documents as Quality System Maturity Indicators

The quality and maintenance of PLCM documents reveals pharmaceutical quality system maturity. Organizations with immature quality systems produce PLCM documents that check regulatory boxes—listing ECs comprehensively with conservative reporting categories, acknowledging required elements, fulfilling submission expectations. But these PLCM documents provide minimal strategic value because they reflect compliance obligation rather than lifecycle management strategy.

Organizations with mature quality systems produce PLCM documents demonstrating sophisticated lifecycle thinking: targeted EC identification justified by process understanding, risk-based reporting category proposals supported by characterization data and PQS capabilities, PACMPs anticipating future manufacturing evolution, and maintained currency through systematic update processes integrated into quality system operations.

This maturity manifests in tangible outcomes. Mature organizations implement post-approval improvements faster because PLCM planning anticipated change types and established appropriate reporting categories. They navigate supplier changes and material shortages more effectively because EC scope acknowledges design space flexibility rather than rigid specification adherence. They demonstrate regulatory inspection resilience because inspectors reviewing PLCM documents find coherent lifecycle strategy supported by robust PQS rather than afterthought compliance artifacts.

The PLCM document, implemented authentically, becomes what it was intended to be: central infrastructure connecting product understanding, control strategy design, risk management, quality systems, and regulatory strategy into integrated lifecycle management capability. Not another form to complete during regulatory preparation, but the strategic framework enabling pharmaceutical organizations to manage commercial manufacturing evolution over decades while assuring consistent product quality and maintaining regulatory compliance.

That’s what ICH Q12 envisions. That’s what the pharmaceutical industry needs. The gap between vision and reality—between PLCM-as-imagined and PLCM-as-done—determines whether these tools transform pharmaceutical lifecycle management or become another layer of regulatory theater generating compliance artifacts without operational value.

Closing that gap requires the same fundamental shift quality culture always requires: moving from procedure compliance and documentation theater toward genuine capability development grounded in understanding, measurement, and continuous improvement. PLCM documents that work emerge from organizations committed to product understanding, lifecycle strategy, and quality system maturity—not from organizations populating templates because ICH Q12 says we should have these documents.

Which type of organization are we building? The answer appears not in the eloquence of our PLCM document prose, but in whether our change control groups reference these documents routinely, whether our annual product reviews assess PLCM currency systematically, whether our quality professionals can articulate EC rationale confidently, and whether our post-approval changes implement predictably because lifecycle planning anticipated them rather than treating each change as crisis requiring regulatory archeology.

PLCM documents are falsifiable quality infrastructure. They make specific predictions: that identified ECs capture elements necessary for quality assurance, that reporting categories align with actual quality risk, that PACMPs enable anticipated changes efficiently, that PQS provides appropriate rigor for internally managed changes. These predictions can be tested through change implementation experience, regulatory inspection outcomes, supply chain resilience during disruptions, and cycle time metrics for post-approval changes.

Organizations serious about pharmaceutical lifecycle management should test these predictions systematically. If PLCM strategies prove ineffective—if supposedly non-critical parameters actually impact quality when changed, if reporting categories prove inappropriate, if PQS rigor proves insufficient for internally managed changes—that’s valuable information demanding revision. If PLCM strategies prove effective, that validates the lifecycle management approach and builds confidence for further refinement.

Most organizations won’t conduct this rigorous testing. PLCM documents will become another compliance artifact, accepted uncritically as required elements without empirical validation of effectiveness. This is exactly the kind of unfalsifiable quality system I’ve critiqued throughout this blog. Genuine commitment to lifecycle management requires honest measurement of whether ICH Q12 tools actually improve lifecycle management outcomes.

The pharmaceutical industry deserves better. Patients deserve better. We can build lifecycle management infrastructure that actually manages lifecycles—or we can generate impressive documents that impress nobody except those who’ve never tried using them for actual change management decisions.

A 2025 Retrospective for Investigations of a Dog

If the history of pharmaceutical quality management were written as a geological timeline, 2025 would hopefully mark the end of the Holocene of Compliance—a long, stable epoch where “following the procedure” was sufficient to ensure survival—and the beginning of the Anthropocene of Complexity.

For decades, our industry has operated under a tacit social contract. We agreed to pretend that “compliance” was synonymous with “quality.” We agreed to pretend that a validated method would work forever because we proved it worked once in a controlled protocol three years ago. We agreed to pretend that “zero deviations” meant “perfect performance,” rather than “blind surveillance.” We agreed to pretend that if we wrote enough documents, reality would conform to them.

If I had my wish 2025 would be the year that contract finally dissolved.

Throughout the year—across dozens of posts, technical analyses, and industry critiques on this blog—I have tried to dismantle the comfortable illusions of “Compliance Theater” and show how this theater collides violently with the unforgiving reality of complex systems.

The connecting thread running through every one of these developments is the concept I have returned to obsessively this year: Falsifiable Quality.

This Year in Review is not merely a summary of blog posts. It is an attempt to synthesize the fragmented lessons of 2025 into a coherent argument. The argument is this: A quality system that cannot be proven wrong is a quality system that cannot be trusted.

If our systems—our validation protocols, our risk assessments, our environmental monitoring programs—are designed only to confirm what we hope is true (the “Happy Path”), they are not quality systems at all. They are comfort blankets. And 2025 was the year we finally started pulling the blanket off.

The Philosophy of Doubt

(Reflecting on: The Effectiveness Paradox, Sidney Dekker, and Gerd Gigerenzer)

Before we dissect the technical failures of 2025, let me first establish the philosophical framework that defined this year’s analysis.

In August, I published “The Effectiveness Paradox: Why ‘Nothing Bad Happened’ Doesn’t Prove Your Quality System Works.” It became one of the most discussed posts of the year because it attacked the most sacred metric in our industry: the trend line that stays flat.

We are conditioned to view stability as success. If Environmental Monitoring (EM) data shows zero excursions for six months, we throw a pizza party. If a method validation passes all acceptance criteria on the first try, we commend the development team. If a year goes by with no Critical deviations, we pay out bonuses.

But through the lens of Falsifiable Quality—a concept heavily influenced by the philosophy of Karl Popper, the challenging insights of Deming, and the safety science of Sidney Dekker, whom we discussed in November—these “successes” look suspiciously like failures of inquiry.

The Problem with Unfalsifiable Systems

Karl Popper famously argued that a scientific theory is only valid if it makes predictions that can be tested and proven false. “All swans are white” is a scientific statement because finding one black swan falsifies it. “God is love” is not, because no empirical observation can disprove it.

In 2025, I argued that most Pharmaceutical Quality Systems (PQS) are designed to be unfalsifiable.

  • The Unfalsifiable Alert Limit: We set alert limits based on historical averages + 3 standard deviations. This ensures that we only react to statistical outliers, effectively blinding us to gradual drift or systemic degradation that remains “within the noise.”
  • The Unfalsifiable Robustness Study: We design validation protocols that test parameters we already know are safe (e.g., pH +/- 0.1), avoiding the “cliff edges” where the method actually fails. We prove the method works where it works, rather than finding where it breaks.
  • The Unfalsifiable Risk Assessment: We write FMEAs where the conclusion (“The risk is acceptable”) is decided in advance, and the RPN scores are reverse-engineered to justify it.

This is “Safety Theater,” a term Dekker uses to describe the rituals organizations perform to look safe rather than be safe.

Safety-I vs. Safety-II

In November’s post “Sidney Dekker: The Safety Scientist Who Influences How I Think About Quality,“ I explored Dekker’s distinction between Safety-I (minimizing things that go wrong) and Safety-II (understanding how things usually go right).

Traditional Quality Assurance is obsessed with Safety-I. We count deviations. We count OOS results. We count complaints. When those counts are low, we assume the system is healthy.
But as the LeMaitre Vascular warning letter showed us this year (discussed in Part III), a system can have “zero deviations” simply because it has stopped looking for them. LeMaitre had excellent water data—because they were cleaning the valves before they sampled them. They were measuring their ritual, not their water.

Falsifiable Quality is the bridge to Safety-II. It demands that we treat every batch record not as a compliance artifact, but as a hypothesis test.

  • Hypothesis: “The contamination control strategy is effective.”
  • Test: Aggressive monitoring in worst-case locations, not just the “representative” center of the room.
  • Result: If we find nothing, the hypothesis survives another day. If we find something, we have successfully falsified the hypothesis—which is a good thing because it reveals reality.

The shift from “fearing the deviation” to “seeking the falsification” is a cultural pivot point of 2025.

The Epistemological Crisis in the Lab (Method Validation)

(Reflecting on: USP <1225>, Method Qualification vs. Validation, and Lifecycle Management)

Nowhere was the battle for Falsifiable Quality fought more fiercely in 2025 than in the analytical laboratory.

The proposed revision to USP <1225> Validation of Compendial Procedures (published in Pharmacopeial Forum 51(6)) arrived late in the year, but it serves as the perfect capstone to the arguments I’ve been making since January.

For forty years, analytical validation has been the ultimate exercise in “Validation as an Event.” You develop a method. You write a protocol. You execute the protocol over three days with your best analyst and fresh reagents. You print the report. You bind it. You never look at it again.

This model is unfalsifiable. It assumes that because the method worked in the “Work-as-Imagined” conditions of the validation study, it will work in the “Work-as-Done” reality of routine QC for the next decade.

The Reportable Result: Validating Decisions, Not Signals

The revised USP <1225>—aligned with ICH Q14(Analytical Procedure Development) and USP <1220> (The Lifecycle Approach)—destroys this assumption. It introduces concepts that force falsifiability into the lab.

The most critical of these is the Reportable Result.

Historically, we validated “the instrument” or “the measurement.” We proved that the HPLC could inject the same sample ten times with < 1.0% RSD.

But the Reportable Result is the final value used for decision-making—the value that appears on the Certificate of Analysis. It is the product of a complex chain: Sampling -> Transport -> Storage -> Preparation -> Dilution -> Injection -> Integration -> Calculation -> Averaging.

Validating the injection precision (the end of the chain) tells us nothing about the sampling variability (the beginning of the chain).

By shifting focus to the Reportable Result, USP <1225> forces us to ask: “Does this method generate decisions we can trust?”

The Replication Strategy: Validating “Work-as-Done”

The new guidance insists that validation must mimic the replication strategy of routine testing.
If your SOP says “We report the average of 3 independent preparations,” then your validation must evaluate the precision and accuracy of that average, not of the individual preparations.

This seems subtle, but it is revolutionary. It prevents the common trick of “averaging away” variability during validation to pass the criteria, only to face OOS results in routine production because the routine procedure doesn’t use the same averaging scheme.

It forces the validation study to mirror the messy reality of the “Work-as-Done,” making the validation data a falsifiable predictor of routine performance, rather than a theoretical maximum capability.

Method Qualification vs. Validation: The June Distinction

I wrote “Method Qualification and Validation,” clarifying a distinction that often confuses the industry.

  • Qualification is the “discovery phase” where we explore the method’s limits. It is inherently falsifiable—we want to find where the method breaks.
  • Validation has traditionally been the “confirmation phase” where we prove it works.

The danger, as I noted in that post, is when we skip the falsifiable Qualification step and go straight to Validation. We write the protocol based on hope, not data.

USP <1225> essentially argues that Validation must retain the falsifiable spirit of Qualification. It is not a coronation; it is a stress test.

The Death of “Method Transfer” as We Know It

In a Falsifiable Quality system, a method is never “done.” The Analytical Target Profile (ATP)—a concept from ICH Q14 that permeates the new thinking—is a standing hypothesis: “This method measures Potency within +/- 2%.”

Every time we run a system suitability check, every time we run a control standard, we are testing that hypothesis.

If the method starts drifting—even if it still passes broad system suitability limits—a falsifiable system flags the drift. An unfalsifiable system waits for the OOS.

The draft revision of USP <1225> is a call to arms. It asks us to stop treating validation as a “ticket to ride”—a one-time toll we pay to enter GMP compliance—and start treating it as a “ticket to doubt.” Validation gives us permission to use the method, but only as long as the data continues to support the hypothesis of fitness.

The Reality Check (The “Unholy Trinity” of Warning Letters)

Philosophy and guidelines are fine, but in 2025, reality kicked in the door. The regulatory year was defined by three critical warning letters—Sanofi, LeMaitre, and Rechon—that collectively dismantled the industry’s illusions of control.

It began, as these things often do, with a ghost from the past.

Sanofi Framingham: The Pendulum Swings Back

(Reflecting on: Failure to Investigate Critical Deviations and The Sanofi Warning Letter)

The year opened with a shock. On January 15, 2025, the FDA issued a warning letter to Sanofi’s Framingham facility—the sister site to the legacy Genzyme Allston landing, whose consent decree defined an entire generation of biotech compliance and of my career.

In my January analysis (“Failure to Investigate Critical Deviations: A Cautionary Tale“), I noted that the FDA’s primary citation was a failure to “thoroughly investigate any unexplained discrepancy.”

This is the cardinal sin of Falsifiable Quality.

An “unexplained discrepancy” is a signal from reality. It is the system telling you, “Your hypothesis about this process is wrong.”

  • The Falsifiable Response: You dive into the discrepancy. You assume your control strategy missed something. You use Causal Reasoning (the topic of my May post) to find the mechanism of failure.
  • The Sanofi Response: As the warning letter detailed, they frequently attributed failures to “isolated incidents” or superficial causes without genuine evidence.

This is the “Refusal to Falsify.” By failing to investigate thoroughly, the firm protects the comfortable status quo. They choose to believe the “Happy Path” (the process is robust) over the evidence (the discrepancy).

The Pendulum of Compliance

In my companion post (“Sanofi Warning Letter”), I discussed the “pendulum of compliance.” The Framingham site was supposed to be the fortress of quality, built on the lessons of the Genzyme crisis.

The failure at Sanofi wasn’t a lack of SOPs; it was a lack of curiosity.

The investigators likely had checklists, templates, and timelines (Compliance Theater), but they lacked the mandate—or perhaps the Expertise —to actually solve the problem.

This set the thematic stage for the rest of 2025. Sanofi showed us that “closing the deviation” is not the same as fixing the problem. This insight led directly into my August argument in “The Effectiveness Paradox“: You can close 100% of your deviations on time and still have a manufacturing process that is spinning out of control.

If Sanofi was the failure of investigation (looking back), Rechon and LeMaitre were failures of surveillance (looking forward). Together, they form a complete picture of why unfalsifiable systems fail.

Reflecting on: Rechon Life Science and LeMaitre Vascular

Philosophy and guidelines are fine, but in September, reality kicked in the door.

Two warning letters in 2025—Rechon Life Science (September) and LeMaitre Vascular (August)—provided brutal case studies in what happens when “representative sampling” is treated as a buzzword rather than a statistical requirement.

Rechon Life Science: The Map vs. The Territory

The Rechon Life Science warning letter was a significant regulatory signal of 2025 regarding sterile manufacturing. It wasn’t just a list of observations; it was an indictment of unfalsifiable Contamination Control Strategies (CCS).

We spent 2023 and 2024 writing massive CCS documents to satisfy Annex 1. Hundreds of pages detailing airflows, gowning procedures, and material flows. We felt good about them. We felt “compliant.”

Then the FDA walked into Rechon and essentially asked: “If your CCS is so good, why does your smoke study show turbulence over the open vials?”

The warning letter highlighted a disconnect I’ve called “The Map vs. The Territory.”

  • The Map: The CCS document says the airflow is unidirectional and protects the product.
  • The Territory: The smoke study video shows air eddying backward from the operator to the sterile core.

In an unfalsifiable system, we ignore the smoke study (or film it from a flattering angle) because it contradicts the CCS. We prioritize the documentation (the claim) over the observation (the evidence).

In a falsifiable system, the smoke study is the test. If the smoke shows turbulence, the CCS is falsified. We don’t defend the CCS; we rewrite it. We redesign the line.

The FDA’s critique of Rechon’s “dynamic airflow visualization” was devastating because it showed that Rechon was using the smoke study as a marketing video, not a diagnostic tool. They filmed “representative” operations that were carefully choreographed to look clean, rather than the messy reality of interventions.

LeMaitre Vascular: The Sin of “Aspirational Data”

If Rechon was about air, LeMaitre Vascular (analyzed in my August post “When Water Systems Fail“) was about water. And it contained an even more egregious sin against falsifiability.

The FDA observed that LeMaitre’s water sampling procedures required cleaning and purging the sample valves before taking the sample.

Let’s pause and consider the epistemology of this.

  • The Goal: To measure the quality of the water used in manufacturing.
  • The Reality: Manufacturing operators do not purge and sanitize the valve for 10 minutes before filling the tank. They open the valve and use the water.
  • The Sample: By sanitizing the valve before sampling, LeMaitre was measuring the quality of the sampling process, not the quality of the water system.

I call this “Aspirational Data.” It is data that reflects the system as we wish it existed, not as it actually exists. It is the ultimate unfalsifiable metric. You can never find biofilm in a valve if you scrub the valve with alcohol before you open it.

The FDA’s warning letter was clear: “Sampling… must include any pathway that the water travels to reach the process.”

LeMaitre also performed an unauthorized “Sterilant Switcheroo,” changing their sanitization agent without change control or biocompatibility assessment. This is the hallmark of an unfalsifiable culture: making changes based on convenience, assuming they are safe, and never designing the study to check if that assumption is wrong.

The “Representative” Trap

Both warning letters pivot on the misuse of the word “representative.”

Firms love to claim their EM sampling locations are “representative.” But representative of what? Usually, they are representative of the average condition of the room—the clean, empty spaces where nothing happens.

But contamination is not an “average” event. It is a specific, localized failure. A falsifiable EM program places probes in the “worst-case” locations—near the door, near the operator’s hands, near the crimping station. It tries to find contamination. It tries to falsify the claim that the zone is sterile, asceptic or bioburden reducing.

When Rechon and LeMaitre failed to justify their sampling locations, they were guilty of designing an unfalsifiable experiment. They placed the “microscope” where they knew they wouldn’t find germs.

2025 taught us that regulators are no longer impressed by the thickness of the CCS binder. They are looking for the logic of control. They are testing your hypothesis. And if you haven’t tested it yourself, you will fail.

The Investigation as Evidence

(Reflecting on: The Golden Start to a Deviation Investigation, Causal Reasoning, Take-the-Best Heuristics, and The Catalent Case)

If Rechon, LeMaitre, and Sanofi teach us anything, it is that the quality system’s ability to discover failure is more important than its ability to prevent failure.

A perfect manufacturing process that no one is looking at is indistinguishable from a collapsing process disguised by poor surveillance. But a mediocre process that is rigorously investigated, understood, and continuously improved is a path toward genuine control.

The investigation itself—how we respond to a deviation, how we reason about causation, how we design corrective actions—is where falsifiable quality either succeeds or fails.

The Golden Day: When Theory Meets Work-as-Done

In April, I published “The Golden Start to a Deviation Investigation,” which made a deceptively simple argument: The first 24 hours after a deviation is discovered are where your quality system either commits to discovering truth or retreats into theater.

This argument sits at the heart of falsifiable quality.

When a deviation occurs, you have a narrow window—what I call the “Golden Day”—where evidence is fresh, memories are intact, and the actual conditions that produced the failure still exist. If you waste this window with vague problem statements and abstract discussions, you permanently lose the ability to test causal hypotheses later.

The post outlined a structured protocol:

First, crystallize the problem. Not “potency was low”—but “Lot X234, potency measured at 87% on January 15th at 14:32, three hours after completion of blending in Vessel C-2.” Precision matters because only specific, bounded statements can be falsified. A vague problem statement can always be “explained away.”

Second, go to the Gemba. This is the antidote to “work-as-imagined” investigation. The SOP says the temperature controller should maintain 37°C +/- 2°C. But the Gemba walk reveals that the probe is positioned six inches from the heating element, the data logger is in a recessed pocket where humidity accumulates, and the operator checks it every four hours despite a requirement to check hourly. These are the facts that predict whether the deviation will recur.

Third, interview with cognitive discipline. Most investigations fail not because investigators lack information, but because they extract information poorly. Cognitive interviewing—developed by the FBI and the National Transportation Safety Board—uses mental reinstatement, multiple perspectives, and sequential reordering to access accurate recall rather than confabulated narrative. The investigator asks the operator to walk through the event in different orders, from different viewpoints, each time triggering different memory pathways. This is not “soft” technique; it is a mechanism for generating falsifiable evidence.

The Golden Day post makes it clear: You do not investigate deviations to document compliance. You investigate deviations to gather evidence about whether your understanding of the process is correct.

Causal Reasoning: Moving Beyond “What Was Missing”

Most investigation tools fail not because they are flawed, but because they are applied with the wrong mindset. In my May post “Causal Reasoning: A Transformative Approach to Root Cause Analysis,” I argued that pharmaceutical investigations are often trapped in “negative reasoning.”

Negative reasoning asks: “What barrier was missing? What should have been done but wasn’t?” This mindset leads to unfalsifiable conclusions like “Procedure not followed” or “Training was inadequate.” These are dead ends because they describe the absence of an ideal, not the presence of a cause.

Causal reasoning flips the script. It asks: “What was present in the system that made the observed outcome inevitable?”

Instead of settling for “human error,” causal reasoning demands we ask: What environmental cues made the action sensible to the operator at that moment? Were the instructions ambiguous? Did competing priorities make compliance impossible? Was the process design fragile?

This shift transforms the investigation from a compliance exercise into a scientific inquiry.

Consider the LeMaitre example:

  • Negative Reasoning: “Why didn’t they sample the true condition?” Answer: “Because they didn’t follow the intent of the sampling plan.”
  • Causal Reasoning: “What made the pre-cleaning practice sensible to them?” Answer: “They believed it ensured sample validity by removing valve residue.”

By understanding the why, we identify a knowledge gap that can be tested and corrected, rather than a negligence gap that can only be punished.

In September, “Take-the-Best Heuristic for Causal Investigation” provided a practical framework for this. Instead of listing every conceivable cause—a process that often leads to paralysis—the “Take-the-Best” heuristic directs investigators to focus on the most information-rich discriminators. These are the factors that, if different, would have prevented the deviation. This approach focuses resources where they matter most, turning the investigation into a targeted search for truth.

CAPA: Predictions, Not Promises

The Sanofi warning letter—analyzed in January—showed the destination of unfalsifiable investigation: CAPAs that exist mainly as paperwork.

Sanofi had investigation reports. They had “corrective actions.” But the FDA noted that deviations recurred in similar patterns, suggesting that the investigation had identified symptoms, not mechanisms, and that the “corrective” action had not actually addressed causation.

This is the sin of treating CAPA as a promise rather than a hypothesis.

A falsifiable CAPA is structured as an explicit prediction: “If we implement X change, then Y undesirable outcome will not recur under conditions Z.”

This can be tested. If it fails the test, the CAPA itself becomes evidence—not of failure, but of incomplete causal understanding. Which is valuable.

In the Rechon analysis, this showed up concretely: The FDA’s real criticism was not just that contamination was found; it was that Rechon’s Contamination Control Strategy had no mechanism to falsify itself. If the CCS said “unidirectional airflow protects the product,” and smoke studies showed bidirectional eddies, the CCS had been falsified. But Rechon treated the falsification as an anomaly to be explained away, rather than evidence that the CCS hypothesis was wrong.

A falsifiable organization would say: “Our CCS predicted that Grade A in an isolator with this airflow pattern would remain sterile. The smoke study proves that prediction wrong. Therefore, the CCS is false. We redesign.”

Instead, they filmed from a different angle and said the aerodynamics were “acceptable.”

Knowledge Integration: When Deviations Become the Curriculum

The final piece of falsifiable investigation is what I call “knowledge integration.” A single deviation is a data point. But across the organization, deviations should form a curriculum about how systems actually fail.

Sanofi’s failure was not that they investigated each deviation badly (though they did). It was that they investigated them in isolation. Each deviation closed on its own. Each CAPA addressed its own batch. There was no organizational learning—no mechanism for a pattern of similar deviations to trigger a hypothesis that the control strategy itself was fundamentally flawed.

This is where the Catalent case study, analyzed in September’s “When 483s Reveal Zemblanity,” becomes instructive. Zemblanity is the opposite of serendipity: the seemingly random recurrence of the same failure through different paths. Catalent’s 483 observations were not isolated mistakes; they formed a pattern that revealed a systemic assumption (about equipment capability, about environmental control, about material consistency) that was false across multiple products and locations.

A falsifiable quality system catches zemblanity early by:

  1. Treating each deviation as a test of organizational hypotheses, not as an isolated incident.
  2. Trending deviation patterns to detect when the same causal mechanism is producing failures across different products, equipment, or operators.
  3. Revising control strategies when patterns falsify the original assumptions, rather than tightening parameters at the margins.

The Digital Hallucination (CSA, AI, and the Expertise Crisis)

(Reflecting on: CSA: The Emperor’s New Clothes, Annex 11, and The Expertise Crisis)

While we battled microbes in the cleanroom, a different battle was raging in the server room. 2025 was the year the industry tried to “modernize” validation through Computer Software Assurance (CSA) and AI, and in many ways, it was the year we tried to automate our way out of thinking.

CSA: The Emperor’s New Validation Clothes

In September, I published “Computer System Assurance: The Emperor’s New Validation Clothes,” a critique of the the contortions being made around the FDA’s guidance. The narrative sold by consultants for years was that traditional Computer System Validation (CSV) was “broken”—too much documentation, too much testing—and that CSA was a revolutionary new paradigm of “critical thinking.”

My analysis showed that this narrative is historically illiterate.

The principles of CSA—risk-based testing, leveraging vendor audits, focusing on intended use—are not new. They are the core principles of GAMP5 and have been applied for decades now.

The industry didn’t need a new guidance to tell us to use critical thinking; we had simply chosen not to use the critical thinking tools we already had. We had chosen to apply “one-size-fits-all” templates because they were safe (unfalsifiable).

The CSA guidance is effectively the FDA saying: “Please read the GAMP5 guide you claimed to be following for the last 15 years.”

The danger of the “CSA Revolution” narrative is that it encourages a swing to the opposite extreme: “Unscripted Testing” that becomes “No Testing.”

In a falsifiable system, “unscripted testing” is highly rigorous—it is an expert trying to break the software (“Ad Hoc testing”). But in an unfalsifiable system, “unscripted testing” becomes “I clicked around for 10 minutes and it looked fine.”

The Expertise Crisis: AI and the Death of the Apprentice

This leads directly to the Expertise Crisis. In September, I wrote “The Expertise Crisis: Why AI’s War on Entry-Level Jobs Threatens Quality’s Future.” This was perhaps the most personal topic I covered this year, because it touches on the very survival of our profession.

We are rushing to integrate Artificial Intelligence (AI) into quality systems. We have AI writing deviations, AI drafting SOPs, AI summarizing regulatory changes. The efficiency gains are undeniable. But the cost is hidden, and it is epistemological.

Falsifiability requires expertise.
To falsify a claim—to look at a draft investigation report and say, “No, that conclusion doesn’t follow from the data”—you need deep, intuitive knowledge of the process. You need to know what a “normal” pH curve looks like so you can spot the “abnormal” one that the AI smoothed over.

Where does that intuition come from? It comes from the “grunt work.” It comes from years of reviewing batch records, years of interviewing operators, years of struggling to write a root cause analysis statement.

The Expertise Crisis is this: If we give all the entry-level work to AI, where will the next generation of Quality Leaders come from?

  • The Junior Associate doesn’t review the raw data; the AI summarizes it.
  • The Junior Associate doesn’t write the deviation; the AI generates the text.
  • Therefore, the Junior Associate never builds the mental models necessary to critique the AI.

The Loop of Unfalsifiable Hallucination

We are creating a closed loop of unfalsifiability.

  1. The AI generates a plausible-sounding investigation report.
  2. The human reviewer (who has been “de-skilled” by years of AI reliance) lacks the deep expertise to spot the subtle logical flaw or the missing data point.
  3. The report is approved.
  4. The “hallucination” becomes the official record.

In a falsifiable quality system, the human must remain the adversary of the algorithm. The human’s job is to try to break the AI’s logic, to check the citations, to verify the raw data.
But in 2025, we saw the beginnings of a “Compliance Autopilot”—a desire to let the machine handle the “boring stuff.”

My warning in September remains urgent: Efficiency without expertise is just accelerated incompetence. If we lose the ability to falsify our own tools, we are no longer quality professionals; we are just passengers in a car driven by a statistical model that doesn’t know what “truth” is.

My post “The Missing Middle in GMP Decision Making: How Annex 22 Redefines Human-Machine Collaboration in Pharmaceutical Quality Assurance” goes a lot deeper here.

Annex 11 and Data Governance

In August, I analyzed the draft Annex 11 (Computerised Systems) in the post “Data Governance Systems: A Fundamental Shift.”

The Europeans are ahead of the FDA here. While the FDA talks about “Assurance” (testing less), the EU is talking about “Governance” (controlling more). The new Annex 11 makes it clear: You cannot validate a system if you do not control the data lifecycle. Validation is not a test script; it is a state of control.

This aligns perfectly with USP <1225> and <1220>. Whether it’s a chromatograph or an ERP system, the requirement is the same: Prove that the data is trustworthy, not just that the software is installed.

The Process as a Hypothesis (CPV & Cleaning)

(Reflecting on: Continuous Process Verification and Hypothesis Formation)

The final frontier of validation we explored in 2025 was the manufacturing process itself.

CPV: Continuous Falsification

In March, I published “Continuous Process Verification (CPV) Methodology and Tool Selection.”
CPV is the ultimate expression of Falsifiable Quality in manufacturing.

  • Traditional Validation (3 Batches): “We made 3 good batches, therefore the process is perfect forever.” (Unfalsifiable extrapolation).
  • CPV: “We made 3 good batches, so we have a license to manufacture, but we will statistically monitor every subsequent batch to detect drift.” (Continuous hypothesis testing).

The challenge with CPV, as discussed in the post, is that it requires statistical literacy. You cannot implement CPV if your quality unit doesn’t understand the difference between Cpk and Ppk, or between control limits and specification limits.

This circles back to the Expertise Crisis. We are implementing complex statistical tools (CPV software) at the exact moment we are de-skilling the workforce. We risk creating a “CPV Dashboard” that turns red, but no one knows why or what to do about it.

Cleaning Validation: The Science of Residue

In August, I tried to apply falsifiability to one of the most stubborn areas of dogma: Cleaning Validation.

In “Building Decision-Making with Structured Hypothesis Formation,“ I argued that cleaning validation should not be about “proving it’s clean.” It should be about “understanding why it gets dirty.”

  • Traditional Approach: Swab 10 spots. If they pass, we are good.
  • Hypothesis Approach: “We hypothesize that the gasket on the bottom valve is the hardest to clean. We predict that if we reduce rinse time by 1 minute, that gasket will fail.”

By testing the boundaries—by trying to make the cleaning fail—we understand the Design Space of the cleaning process.

We discussed the “Visual Inspection” paradox in cleaning: If you can see the residue, it failed. But if you can’t see it, does it pass?

Only if you have scientifically determined the Visible Residue Limit (VRL). Using “visually clean” without a validated VRL is—you guessed it—unfalsifiable.

To: Jeremiah Genest
From: Perplexity Research
Subject: Draft Content – Single-Use Systems & E&L Section

Here is a section on Single-Use Systems (SUS) and Extractables & Leachables (E&L).

I have positioned this piece to bridge the gap between “Part III: The Reality Check” (Contamination/Water) and “Part V: The Process as a Hypothesis” (Cleaning Validation).

The argument here is that by switching from Stainless Steel to Single-Use, we traded a visible risk (cleaning residue) for an invisible one (chemical migration), and that our current approach to E&L is often just “Paper Safety”—relying on vendor data that doesn’t reflect the “Work-as-Done” reality of our specific process conditions.

The Plastic Paradox (Single-Use Systems and the E&L Mirage)

If the Rechon and LeMaitre warning letters were about the failure to control biological contaminants we can find, the industry’s struggle with Single-Use Systems (SUS) in 2025 was about the chemical contaminants we choose not to find.

We have spent the last decade aggressively swapping stainless steel for plastic. The value proposition was irresistible: Eliminate cleaning validation, eliminate cross-contamination, increase flexibility. We traded the “devil we know” (cleaning residue) for the “devil we don’t” (Extractables and Leachables).

But in 2025, with the enforcement reality of USP <665> (Plastic Components and Systems) settling in, we had to confront the uncomfortable truth: Most E&L risk assessments are unfalsifiable.

The Vendor Data Trap

The standard industry approach to E&L is the ultimate form of “Compliance Theater.”

  1. We buy a single-use bag.
  2. We request the vendor’s regulatory support package (the “Map”).
  3. We see that the vendor extracted the film with aggressive solvents (ethanol, hexane) for 7 days.
  4. We conclude: “Our process uses water for 24 hours; therefore, we are safe.”

This logic is epistemologically bankrupt. It assumes that the Vendor’s Model (aggressive solvents/short time) maps perfectly to the User’s Reality (complex buffers/long duration/specific surfactants).

It ignores the fact that plastics are dynamic systems. Polymers age. Gamma irradiation initiates free radical cascades that evolve over months. A bag manufactured in January might have a different leachable profile than a bag manufactured in June, especially if the resin supplier made a “minor” change that didn’t trigger a notification.

By relying solely on the vendor’s static validation package, we are choosing not to falsify our safety hypothesis. We are effectively saying, “If the vendor says it’s clean, we will not look for dirt.”

USP <665>: A Baseline, Not a Ceiling

The full adoption of USP <665> was supposed to bring standardization. And it has—it provides a standard set of extraction conditions. But standards can become ceilings.

In 2025, I observed a troubling trend of “Compliance by Citation.” Firms are citing USP <665> compliance as proof of absence of risk, stopping the inquiry there.

A Falsifiable E&L Strategy goes further. It asks:

  • “What if the vendor data is irrelevant to my specific surfactant?”
  • “What if the gamma irradiation dose varied?”
  • “What if the interaction between the tubing and the connector creates a new species?”

The Invisible Process Aid

We must stop viewing Single-Use Systems as inert piping. They are active process components. They are chemically reactive vessels that participate in our reaction kinetics.

When we treat them as inert, we are engaging in the same “Aspirational Thinking” that LeMaitre used on their water valves. We are modeling the system we want (pure, inert plastic), not the system we have (a complex soup of antioxidants, slip agents, and degradants).

The lesson of 2025 is that Material Qualification cannot be a paper exercise. If you haven’t done targeted simulation studies that mimic your actual “Work-as-Done” conditions, you haven’t validated the system. You’ve just filed the receipt.

The Mandate for 2026

As we look toward 2026, the path is clear. We cannot go back to the comfortable fiction of the pre-2025 era.

The regulatory environment (Annex 1, ICH Q14, USP <1225>, Annex 11) is explicitly demanding evidence of control, not just evidence of compliance. The technological environment (AI) is demanding that we sharpen our human expertise to avoid becoming obsolete. The physical environment (contamination, supply chain complexity) is demanding systems that are robust, not just rigid.

The mandate for the coming year is to build Falsifiable Quality Systems.

What does that look like practically?

  1. In the Lab: Implement USP <1225> logic now. Don’t wait for the official date. Validate your reportable results. Add “challenge tests” to your routine monitoring.
  2. In the Plant: Redesign your Environmental Monitoring to hunt for contamination, not to avoid it. If you have a “perfect” record in a Grade C area, move the plates until you find the dirt.
  3. In the Office: Treat every investigation as a chance to falsify the control strategy. If a deviation occurs that the control strategy said was impossible, update the control strategy.
  4. In the Culture: Reward the messenger. The person who finds the crack in the system is not a troublemaker; they are the most valuable asset you have. They just falsified a false sense of security.
  5. In Design: Embrace the “Elegant Quality System“ (discussed in May). Complexity is the enemy of falsifiability. Complex systems hide failures; simple, elegant systems reveal them.

2025 was the year we stopped pretending. 2026 must be the year we start building. We must build systems that are honest enough to fail, so that we can build processes that are robust enough to endure.

Thank you for reading, challenging, and thinking with me this year. The investigation continues.

Beyond Malfunction Mindset: Normal Work, Adaptive Quality, and the Future of Pharmaceutical Problem-Solving

Beyond the Shadow of Failure

Problem-solving is too often shaped by the assumption that the system is perfectly understood and fully specified. If something goes wrong—a deviation, a batch out-of-spec, or a contamination event—our approach is to dissect what “failed” and fix that flaw, believing this will restore order. This way of thinking, which I call the malfunction mindset, is as ingrained as it is incomplete. It assumes that successful outcomes are the default, that work always happens as written in SOPs, and that only failure deserves our scrutiny.

But here’s the paradox: most of the time, our highly complex manufacturing environments actually succeed—often under imperfect, shifting, and not fully understood conditions. If we only study what failed, and never question how our systems achieve their many daily successes, we miss the real nature of pharmaceutical quality: it is not the absence of failure, but the presence of robust, adaptive work. Taking this broader, more nuanced perspective is not just an academic exercise—it’s essential for building resilient operations that truly protect patients, products, and our organizations.

Drawing from my thinking through zemblanity (the predictable but often overlooked negative outcomes of well-intentioned quality fixes), the effectiveness paradox (why “nothing bad happened” isn’t proof your quality system works), and the persistent gap between work-as-imagined and work-as-done, this post explores why the malfunction mindset persists, how it distorts investigations, and what future-ready quality management should look like.

The Allure—and Limits—of the Failure Model

Why do we reflexively look for broken parts and single points of failure? It is, as Sidney Dekker has argued, both comforting and defensible. When something goes wrong, you can always point to a failed sensor, a missed checklist, or an operator error. This approach—introducing another level of documentation, another check, another layer of review—offers a sense of closure and regulatory safety. After all, as long as you can demonstrate that you “fixed” something tangible, you’ve fulfilled investigational due diligence.

Yet this fails to account for how quality is actually produced—or lost—in the real world. The malfunction model treats systems like complicated machines: fix the broken gear, oil the creaky hinge, and the machine runs smoothly again. But, as Dekker reminds us in Drift Into Failure, such linear thinking ignores the drift, adaptation, and emergent complexity that characterize real manufacturing environments. The truth is, in complex adaptive systems like pharmaceutical manufacturing, it often takes more than one “error” for failure to manifest. The system absorbs small deviations continuously, adapting and flexing until, sometimes, a boundary is crossed and a problem surfaces.

W. Edwards Deming’s wisdom rings truer than ever: “Most problems result from the system itself, not from individual faults.” A sustainable approach to quality is one that designs for success—and that means understanding the system-wide properties enabling robust performance, not just eliminating isolated malfunctions.

Procedural Fundamentalism: The Work-as-Imagined Trap

One of the least examined, yet most impactful, contributors to the malfunction mindset is procedural fundamentalism—the belief that the written procedure is both a complete specification and an accurate description of work. This feels rigorous and provides compliance comfort, but it is a profound misreading of how work actually happens in pharmaceutical manufacturing.

Work-as-imagined, as elucidated by Erik Hollnagel and others, represents an abstraction: it is how distant architects of SOPs visualize the “correct” execution of a process. Yet, real-world conditions—resource shortages, unexpected interruptions, mismatched raw materials, shifting priorities—force adaptation. Operators, supervisors, and Quality professionals do not simply “follow the recipe”: they interpret, improvise, and—crucially—adjust on the fly.

When we treat procedures as authoritative descriptions of reality, we create the proxy problem: our investigations compare real operations against an imagined baseline that never fully existed. Deviations become automatically framed as problem points, and success is redefined as rigid adherence, regardless of context or outcome.

Complexity, Performance Variability, and Real Success

So, how do pharmaceutical operations succeed so reliably despite the ever-present complexity and variability of daily work?

The answer lies in embracing performance variability as a feature of robust systems, not a flaw. In high-reliability environments—from aviation to medicine to pharmaceutical manufacturing—success is routinely achieved not by demanding strict compliance, but by cultivating adaptive capacity.

Consider environmental monitoring in a sterile suite: The procedure may specify precise times and locations, but a seasoned operator, noticing shifts in people flow or equipment usage, might proactively sample a high-risk area more frequently. This adaptation—not captured in work-as-imagined—actually strengthens data integrity. Yet, traditional metrics would treat this as a procedural deviation.

This is the paradox of the malfunction mindset: in seeking to eliminate all performance variability, we risk undermining precisely those adaptive behaviors that produce reliable quality under uncertainty.

Why the Malfunction Mindset Persists: Cognitive Comfort and Regulatory Reinforcement

Why do organizations continue to privilege the malfunction mindset, even as evidence accumulates of its limits? The answer is both psychological and cultural.

Component breakdown thinking is psychologically satisfying—it offers a clear problem, a specific cause, and a direct fix. For regulatory agencies, it is easy to measure and audit: did the deviation investigation determine the root cause, did the CAPA address it, does the documentation support this narrative? Anything that doesn’t fit this model is hard to defend in audits or inspections.

Yet this approach offers, at best, a partial diagnosis and, at worst, the illusion of control. It encourages organizations to catalog deviations while blindly accepting a much broader universe of unexamined daily adaptations that actually determine system robustness.

Complexity Science and the Art of Organizational Success

To move toward a more accurate—and ultimately more effective—model of quality, pharmaceutical leaders must integrate the insights of complexity science. Drawing from the work of Stuart Kauffman and others at the Santa Fe Institute, we understand that the highest-performing systems operate not at the edge of rigid order, but at the “edge of chaos,” where structure is balanced with adaptability.

In these systems, success and failure both arise from emergent properties—the patterns of interaction between people, procedures, equipment, and environment. The most meaningful interventions, therefore, address how the parts interact, not just how each part functions in isolation.

This explains why traditional root cause analysis, focused on the parts, often fails to produce lasting improvements; it cannot account for outcomes that emerge only from the collective dynamics of the system as a whole.

Investigating for Learning: The Take-the-Best Heuristic

A key innovation needed in pharmaceutical investigations is a shift to what Hollnagel calls Safety-II thinking: focusing on how things go right as well as why they occasionally go wrong.

Here, the take-the-best heuristic becomes crucial. Instead of compiling lists of all deviations, ask: Among all contributing factors, which one, if addressed, would have the most powerful positive impact on future outcomes, while preserving adaptive capacity? This approach ensures investigations generate actionable, meaningful learning, rather than feeding the endless paper chase of “compliance theater.”

Building Systems That Support Adaptive Capability

Taking complexity and adaptive performance seriously requires practical changes to how we design procedures, train, oversee, and measure quality.

  • Procedure Design: Make explicit the distinction between objectives and methods. Procedures should articulate clear quality goals, specify necessary constraints, but deliberately enable workers to choose methods within those boundaries when faced with new conditions.
  • Training: Move beyond procedural compliance. Develop adaptive expertise in your staff, so they can interpret and adjust sensibly—understanding not just “what” to do, but “why” it matters in the bigger system.
  • Oversight and Monitoring: Audit for adaptive capacity. Don’t just track “compliance” but also whether workers have the resources and knowledge to adapt safely and intelligently. Positive performance variability (smart adaptations) should be recognized and studied.
  • Quality System Design: Build systematic learning from both success and failure. Examine ordinary operations to discern how adaptive mechanisms work, and protect these capabilities rather than squashing them in the name of “control.”

Leadership and Systems Thinking

Realizing this vision depends on a transformation in leadership mindset—from one seeking control to one enabling adaptive capacity. Deming’s profound knowledge and the principles of complexity leadership remind us that what matters is not enforcing ever-stricter compliance, but cultivating an organizational context where smart adaptation and genuine learning become standard.

Leadership must:

  • Distinguish between complicated and complex: Apply detailed procedures to the former (e.g., calibration), but support flexible, principles-based management for the latter.
  • Tolerate appropriate uncertainty: Not every problem has a clear, single answer. Creating psychological safety is essential for learning and adaptation during ambiguity.
  • Develop learning organizations: Invest in deep understanding of operations, foster regular study of work-as-done, and celebrate insights from both expected and unexpected sources.

Practical Strategies for Implementation

Turning these insights into institutional practice involves a systematic, research-inspired approach:

  • Start procedure development with observation of real work before specifying methods. Small scale and mock exercises are critical.
  • Employ cognitive apprenticeship models in training, so that experience, reasoning under uncertainty, and systems thinking become core competencies.
  • Begin investigations with appreciative inquiry—map out how the system usually works, not just how it trips up.
  • Measure leading indicators (capacity, information flow, adaptability) not just lagging ones (failures, deviations).
  • Create closed feedback loops for corrective actions—insisting every intervention be evaluated for impact on both compliance and adaptive capacity.

Scientific Quality Management and Adaptive Systems: No Contradiction

The tension between rigorous scientific quality management (QbD, process validation, risk management frameworks) and support for adaptation is a false dilemma. Indeed, genuine scientific quality management starts with humility: the recognition that our understanding of complex systems is always partial, our controls imperfect, and our frameworks provisional.

A falsifiable quality framework embeds learning and adaptation at its core—treating deviations as opportunities to test and refine models, rather than simply checkboxes to complete.

The best organizations are not those that experience the fewest deviations, but those that learn fastest from both expected and unexpected events, and apply this knowledge to strengthen both system structure and adaptive capacity.

Embracing Normal Work: Closing the Gap

Normal pharmaceutical manufacturing is not the story of perfect procedural compliance; it’s the story of people, working together to achieve quality goals under diverse, unpredictable, and evolving conditions. This is both more challenging—and more rewarding—than any plan prescribed solely by SOPs.

To truly move the needle on pharmaceutical quality, organizations must:

  • Embrace performance variability as evidence of adaptive capacity, not just risk.
  • Investigate for learning, not blame; study success, not just failure.
  • Design systems to support both structure and flexible adaptation—never sacrificing one entirely for the other.
  • Cultivate leadership that values humility, systems thinking, and experimental learning, creating a culture comfortable with complexity.

This approach will not be easy. It means questioning decades of compliance custom, organizational habit, and intellectual ease. But the payoff is immense: more resilient operations, fewer catastrophic surprises, and, above all, improved safety and efficacy for the patients who depend on our products.

The challenge—and the opportunity—facing pharmaceutical quality management is to evolve beyond compliance theater and malfunction thinking into a new era of resilience and organizational learning. Success lies not in the illusory comfort of perfectly executed procedures, but in the everyday adaptations, intelligent improvisation, and system-level capabilities that make those successes possible.

The call to action is clear: Investigate not just to explain what failed, but to understand how, and why, things so often go right. Protect, nurture, and enhance the adaptive capacities of your organization. In doing so, pharmaceutical quality can finally become more than an after-the-fact audit; it will become the creative, resilient capability that patients, regulators, and organizations genuinely want to hire.

Recent Podcast Appearance: Risk Revolution

I’m excited to share that I recently had the opportunity to appear on the Risk Revolution podcast, joining host Valerie Mulholland for what turned out to be a provocative and deeply engaging conversation about the future of pharmaceutical quality management.

The episode, titled “Quality Theatre to Quality Science – Jeremiah Genest’s Playbook,” aired on September 28, 2025, and dives into one of my core arguments: that quality systems should be designed to fail predictably so we can learn purposefully. This isn’t about celebrating failure—it’s about building systems intelligent enough to fail in ways that generate learning rather than hiding in the shadows until catastrophic breakdown occurs.

Why This Conversation Matters

Valerie and I spent over an hour exploring what I call “intelligent failure”—a concept that challenges the feel-good metrics that dominate our industry dashboards. You know the ones I’m talking about: those green lights celebrating zero deviations that make everyone feel accomplished while potentially masking the unknowns lurking beneath the surface. As I argued in the episode, these metrics can hide systemic problems rather than prove actual control.

This discussion connects directly to themes I’ve been developing here on Investigations of a Dog, particularly my thoughts on the effectiveness paradox and the dangerous comfort of “nothing bad happened” thinking. The podcast gave me a chance to explore how zemblanity—the patterned recurrence of unfortunate events that we should have anticipated—manifests in quality systems that prioritize the appearance of control over genuine understanding.

The Perfect Platform for These Ideas

Risk Revolution proved to be the ideal venue for this conversation. Valerie brings over 25 years of hands-on experience across biopharmaceutical, pharmaceutical, medical device, and blood transfusion industries, but what sets her apart is her unique combination of practical expertise and cutting-edge research.

The podcast’s monthly format allows for the kind of deep, nuanced discussions that advance risk management maturity rather than recycling conference presentations. When I wrote about Valerie’s writing on the GI Joe Bias, I noted how her emphasis on systematic interventions rather than individual awareness represents exactly the kind of sophisticated thinking our industry needs. This podcast appearance let us explore these concepts in real-time conversation.

What made the discussion particularly engaging was Valerie’s ability to challenge my thinking while building on it. Her research-backed insights into cognitive bias management created a perfect complement to my practical experience with system failures and investigation patterns. We explored how quality professionals—precisely because of our expertise—become vulnerable to specific blind spots that systematic design can address.

Looking Forward

This Risk Revolution appearance represents more than just a podcast interview—it’s part of a broader conversation about advancing pharmaceutical quality management beyond surface-level compliance toward genuine excellence. The episode includes references to my blog work, the Deming philosophy, and upcoming industry conferences where these ideas will continue to evolve.

If you’re interested in how quality systems can be designed for intelligent learning rather than elegant hiding, this conversation offers both provocative challenges and practical frameworks. Fair warning: you might never look at a green dashboard the same way again.

The episode is available now, and I’d love to hear your thoughts on how we might move from quality theatre toward quality science in your own organization.